Skip to Content
  • 4.5
    Impact Factor
  • 4.5
    CiteScore
  • 26 days
    Submission to First Decision
  • 4 days
    Acceptance to Publication

Advances in Respiratory Medicine

Advances in Respiratory Medicine (ARM) is an international, peer-reviewed, open access journal on respiratory medicine, covering allergology, oncology, immunology and infectious diseases of the respiratory system, published bimonthly online. It is the official journal of the Polish Respiratory Society (PtChP). Society members receive discounts on the article processing charges.
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
  • High Visibility: indexed within Scopus, ESCI (Web of Science), PubMed, MEDLINE, PMC, Embase, and other databases. 
  • Journal Rank: JCR - Q1 (Respiratory System) / CiteScore - Q2 (Pulmonary and Respiratory Medicine).
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 25.7 days after submission; acceptance to publication is undertaken in 3.9 days (median values for papers published in this journal in the first half of 2026).
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (1,698)

  • Article
  • Open Access

Background: Experimental data suggest that eosinophils may restrain osteoclastogenesis through eosinophil peroxidase, supporting a potential bone-protective role, whereas human genetic studies have suggested an opposing association. Whether circulating eosinophils are associated with bone mineral density (BMD) in humans, and how corticosteroid exposure modifies this relationship, remains unclear. Methods: We analyzed five cycles of the US National Health and Nutrition Examination Survey (2005–2006, 2007–2008, 2009–2010, 2013–2014, and 2017–2018), including 11,146 adults aged ≥50 years with dual-energy X-ray absorptiometry and complete blood count data. Survey-weighted linear regression was used to model femoral neck BMD as a function of blood eosinophil count, with adjustment for demographic and clinical covariates, four route-specific corticosteroid exposure variables, and eleven classes of bone-active medications. Results: Blood eosinophil count was not associated with femoral neck BMD in the overall population (β = +0.00027 g/cm2 per 100 cells/µL; 95% CI −0.00105 to +0.00159). However, the association differed according to asthma status (interaction β = −0.00438; p = 0.009), whereas no interaction was observed for COPD (p = 0.49). Among participants with asthma, higher eosinophil counts were associated with lower BMD among inhaled corticosteroid users (β = −0.00999 g/cm2 per 100 cells/µL; p = 0.008), whereas no significant association was observed among participants receiving no corticosteroid therapy by any route (β = −0.00159; p = 0.452). An exploratory eosinophil-by-inhaled-corticosteroid interaction was also observed (β = −0.01045; 95% CI −0.01910 to −0.00181; p = 0.019) and persisted among the 925 participants reporting current asthma (p = 0.027). The 282 inhaled corticosteroid users had 80% power only for differences of approximately 0.010 g/cm2 per 100 cells/µL or larger, so that estimate is likely to overstate any true association. In age-stratified analyses the inverse association within asthma was apparent only at age ≥ 75 years (β = −0.01065; p = 0.020), with a non-significant eosinophil-by-age interaction (p = 0.096). Conclusions: Blood eosinophil count was not associated with femoral neck BMD in the overall population. Among participants with asthma, higher eosinophil counts were associated with lower BMD, with exploratory evidence of effect modification by inhaled corticosteroid use. Whether this association reflects eosinophilic inflammation, asthma severity or treatment-related factors remains uncertain. Prospective validation is warranted. The inhaled corticosteroid interaction was not prespecified and is hypothesis-generating.

Adv. Respir. Med.

17 November 2026

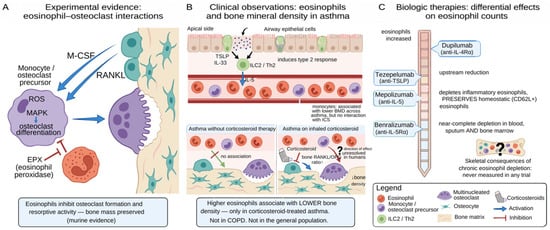
The eosinophil–bone axis and the discrepancy between experimental and human evidence. (A) In mice, eosinophils within the bone marrow niche release eosinophil peroxidase (EPX), which suppresses reactive oxygen species generation and mitogen-activated protein kinase signaling in osteoclast precursors, thereby limiting osteoclast differentiation and bone-resorptive activity [1]. (B) In human type 2 asthma, epithelial alarmins activate ILC2 and Th2 pathways, while IL-5 promotes eosinophil production and release into the circulation, and monocytes provide the precursor pool for osteoclast differentiation. In the present analysis, the inverse association between blood eosinophil count and bone mineral density was most evident among participants receiving inhaled corticosteroids and was not detected in those with no corticosteroid exposure. Inhaled corticosteroid therapy is therefore depicted as the clinical context in which the eosinophil–BMD association emerged, rather than as an independent additive determinant of lower BMD, as inhaled corticosteroid use itself was not independently associated with BMD in this cohort. (C) Available biologic therapies differ substantially in their effects on circulating and tissue eosinophils, ranging from a transient increase in blood eosinophils with dupilumab to near-complete depletion of eosinophils in blood, sputum and bone marrow with benralizumab. To date, no trial of an interleukin-5 pathway biologic has reported skeletal outcomes.
  • Article
  • Open Access

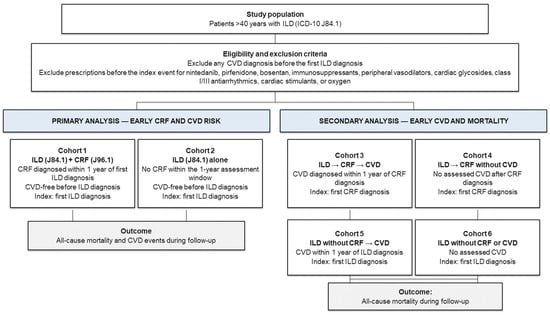
Background/Objective. Interstitial lung diseases (ILD) may be associated with chronic respiratory failure (CRF) and/or cardiovascular diseases (CVD) such as Pulmonary Hypertension, Ischemic Heart Diseases, Heart Failure, and Atrial Arrhythmias. Our research questions were: Does early CRF affect the mortality risk, and timing of the above CVD? Do CVD influence mortality in people with ILD? Methods. We conducted a seven-year, retrospective, observational, multicentre study comparing participants with ILD and early CRF (Cohort 1) and those with ILD alone (Cohort 2) (2392 participants in each cohort). We also assessed the effect of early CVD on mortality risk. Results. The cumulative incidence of death was 65.84% and 38.27% (p < 0.01), while that of any CVD was 79.31% and 46.19% (p < 0.01) for Cohorts 1 and 2, respectively. The time to and cumulative incidence of each of the above CVD were higher in Cohort 1 than in Cohort 2 (all p < 0.001). Incident cardiovascular events were associated with a higher and earlier risk of death in people without but not in those with ILD and early CRF, indicating that CRF plays a role in mortality rates, regardless of those of CVD. Conclusions. Our study suggests an association between chronic respiratory failure, cardiovascular events, and mortality, although it cannot prove causality. These findings indicate the need for structured lung function assessment and closer cardiovascular surveillance in people with ILD, particularly in those developing chronic respiratory failure.

Adv. Respir. Med.

11 November 2026

Cohort Construction Diagram.
  • Review
  • Open Access

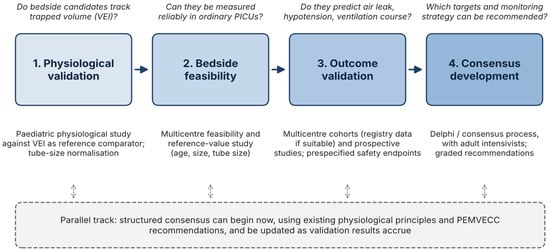
Pediatric acute respiratory distress syndrome (PARDS) has an international, evidence-graded consensus guideline (PALICC-2). PALICC-2 excludes respiratory failure caused solely by airway obstruction. The Paediatric Mechanical Ventilation Consensus Conference (PEMVECC) provides general recommendations for obstructive airway disease, and the 2025 AARC/PALISI guideline on paediatric critical asthma does not address invasive ventilation. Validated, outcome-linked ventilator targets for critical asthma and a severity metric for the intubated child are still missing. This narrative review examines five possible explanations: heterogeneity of obstruction and overlap with parenchymal disease; loss of severity assessment after intubation; the small number of ventilated children; a haemodynamic hazard that develops over minutes to hours; and the brevity and instability of the illness. Adult critical care has the same gap. We pay most attention to the missing severity metric, a daily obstacle for clinicians, although solving it would not alone produce a guideline. We propose a research framework in which physiological validation and consensus development proceed in parallel. PARDS is used only as a comparator; the two conditions are distinct diseases.

Adv. Respir. Med.

10 November 2026

Proposed evidence-development pathway for ventilator targets in paediatric critical asthma. VEI, end-inspiratory lung volume above functional residual capacity; PEMVECC, Paediatric Mechanical Ventilation Consensus Conference.
  • Systematic Review
  • Open Access

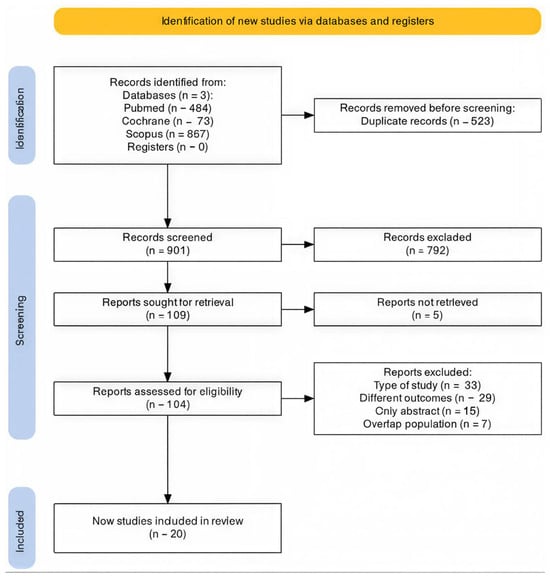
Introduction: Bronchial thermoplasty (BT) reduces airway smooth muscle and may benefit severe asthma, but its role alongside biologics remains unclear. We assessed randomised and real-world evidence on efficacy and safety. Methods: We searched PubMed, Scopus, and Cochrane Library for RCTs and observational studies of BT in adults with severe uncontrolled asthma, analysing them separately. Results: Twenty studies were included (five RCTs, 15 observational). In RCTs, BT improved asthma-related quality of life (AQLQ;MD, 0.69; 95% CI 0.30–1.09), asthma control (ACQ; MD,−0.64; 95%CI, −1.10 to −0.19), and morning peak expiratory flow (MD, 20.62 L/min; 95% CI, 4.92–36.32), but did not improve rescue medication use or symptom-free-days. BT increased the risk of hospitalisation during the treatment period (RR, 3.50; 95%CI, 1.26–9.68), with no significant excess thereafter. Real-world studies showed improvements in AQLQ (MD,1.38; 95%CI, 0.97–1.80), ACQ (MD,−1.24; 95%CI, −1.86 to −0.62), and annualised exacerbation rates (MD, −3.79 exacerbations/patient-year; 95%CI, −6.98 to −0.61). Evidence suggested a possible, inconsistent corticosteroid-sparing effect; data on biologics and long-term safety were limited. Conclusions: BT improved asthma-related quality of life and control, mainly in trials without sham controls, but increased short-term hospitalisation risk. Real-world findings were similar but came from uncontrolled studies. BT is not an established alternative to biologics, but may suit carefully selected patients with severe asthma who cannot use or do not respond to them.

Adv. Respir. Med.

21 October 2026

PRISMA flow diagram of study screening and selection.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
Adv. Respir. Med. - ISSN 2543-6031