


Simple Summary
Glioblastoma is one of the most aggressive brain tumors, with poor survival and early recurrence rates. The development of effective immunotherapy treatments has been limited by the infiltration-resistant and immunosuppressive tumor microenvironments of these tumors. γδ T cells are unconventional T cells that have the potential to overcome these challenges through their unique recognition of molecular targets on glioblastoma cells. Nonetheless, challenges exist in the utilization of these cells, including their isolation, expansion, and potential for protumor activity. In this review, we discuss the biology of γδ T cells and their role in immunotherapy for glioblastoma and propose several research avenues for future studies.
Abstract
Cell-based immunotherapy for glioblastoma (GBM) encounters major challenges due to the infiltration-resistant and immunosuppressive tumor microenvironment (TME). γδ T cells, unconventional T cells expressing the characteristic γδ T cell receptor, have demonstrated promise in overcoming these challenges, suggesting great immunotherapeutic potential. This review presents the role of γδ T cells in GBM and proposes several research avenues for future studies. Using the PubMed, ScienceDirect, and JSTOR databases, we performed a review of the literature studying the biology of γδ T cells and their role in GBM treatment. We identified 15 studies focused on γδ T cells in human GBM. Infiltrative γδ T cells can incite antitumor immune responses in certain TMEs, though rapid tumor progression and TME hypoxia may impact the extent of tumor suppression. In the studies, available findings have shown both the potential for robust antitumor activity and the risk of protumor activity. While γδ T cells have potential as a therapeutic agent against GBM, the technical challenges of extracting, isolating, and expanding γδ T cells, and the activation of antitumoral versus protumoral cascades, remain barriers to their application. Overcoming these limitations may transform γδ T cells into a promising immunotherapy in GBM.
1. Introduction
Glioblastoma (GBM) is among the most aggressive brain tumors, possessing a poor survival rate upon diagnosis and virtually always recurring [1]. The pervasive infiltration of GBM in the brain often precludes complete removal through surgical means. Thus, a wide modality of approaches, including radiation, chemotherapy, targeted therapies, electric fields, and immunotherapy, are used to increase survival [2,3]. GBM immunotherapy has faced severe challenges in successfully reaching and eliminating cancerous cells due to immunosuppression from the GBM tumor microenvironment (TME) and the prevalence of immune escape mechanisms [4,5]. The deep penetration of GBM and the physical limitations imposed by the blood–brain barrier make it difficult for peripheral immune cells to reach the tumors. Those immune cells that do successfully infiltrate tumors are subsequently hindered by the immunosuppressive and hypoxic conditions of the GBM TME [6]. GBM cells can also escape the immune response by shedding existing major histocompatibility complex (MHC) class I proteins, which conventional immune cells depend on for recognition by MHC antigen presentation [4]. Therefore, new strategies of immunotherapy for GBM are needed to address these existing challenges.
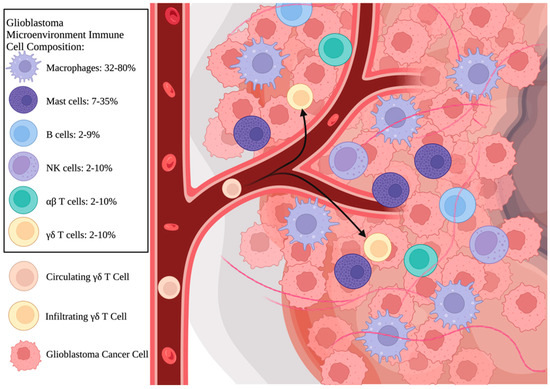
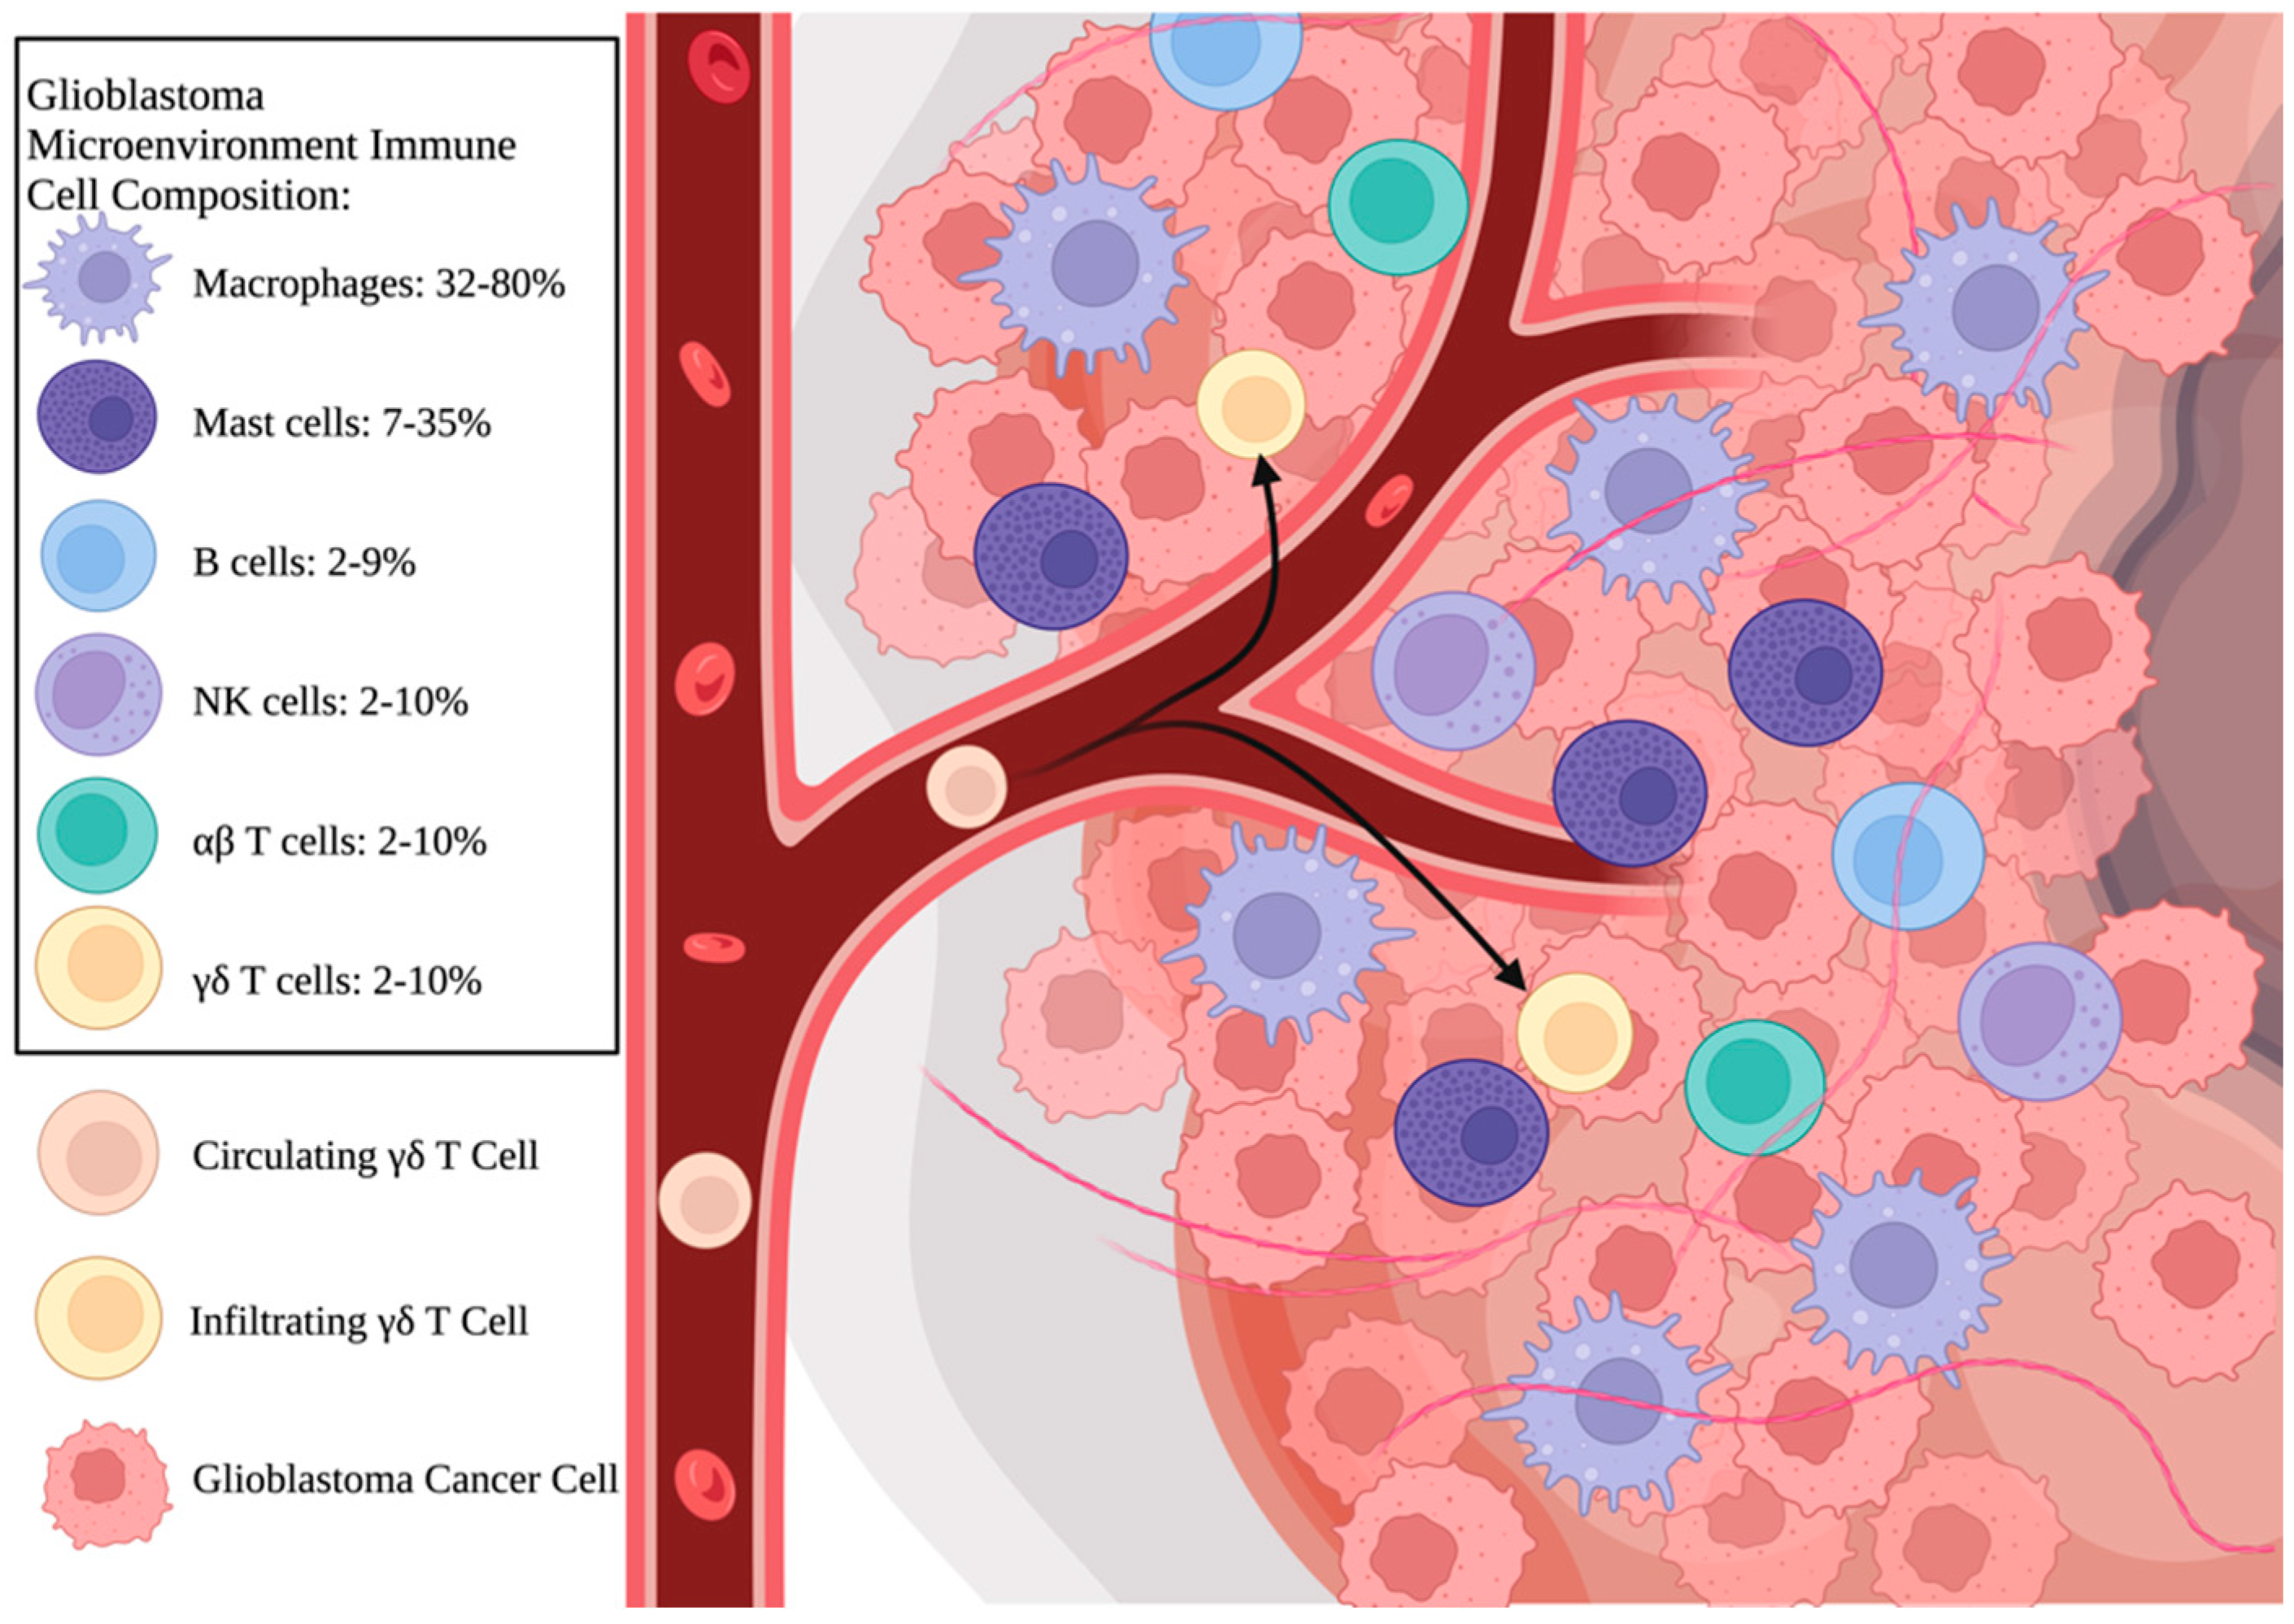
A compelling avenue of immunotherapy utilizes γδ T cells, which do not rely on MHC recognition, to enact immune responses. γδ T cells are unconventional T cells characterized by their expression of the γδ T cell receptor (γδTCR). The novel application of γδ T cells to immunotherapy has shown promise due to their ability to infiltrate a wide variety of tumors with potentially less risk of MHC immune evasion [7]. These unique T cells can commonly be found among tumor-infiltrating leukocytes (TILs) and have exhibited strong natural cytotoxicity towards a variety of solid and circulating cancers, including GBM (Figure 1) [8]. Studying the interaction between the GBM TME and infiltrating γδ T cells can benefit our understanding of GBM pathogenesis, progression, and response to treatment. Moreover, γδ T cells possess great potential as therapeutic agents, and the study of circulating γδ T cells can be utilized in the development of new cell-based therapies. This review examines the role of γδ T cells in GBM, evaluates their utility in cellular-based therapies, and highlights potential future directions (Supplementary Figure S1).
Figure 1.
Illustration of γδ T cell recruitment into the GBM microenvironment. The GBM tumor microenvironment is composed of a diverse array of tumor-infiltrating leukocytes (TILs), which are recruited to the tumor in response to tumor-associated antigens. Macrophages make up the bulk (32–80%) of the GBM TIL population, followed by mast cells (7–35%). NK cells and T cells combined comprise 6–30% of TILs, and B cells make up less than 10%. Among infiltrating T cells, the ratio of αβ to γδ T cells is estimated to be approximately equal. Circulating γδ T cells migrate to tumors through TCR-mediated recognition of tumor antigens. Once recruited, the circulating lymphocytes penetrate through the blood vessels and enter the tumors, where they become infiltrating γδ T cells. The percentages used are estimates drawn from reference material published by Lee et al. and are consistent with prior published reports [9,10,11,12,13]. Created with BioRender.com and published with permission.
2. Introduction to γδ T Cells
γδ T cells are innate lymphocytes with a TCR composed of γ and δ chains, unlike the chains that comprise most TCRs [14]. They have immense structural and functional heterogeneity and can recognize a wide array of different ligands. Due to the antigenic diversity, γδ T cells employ various TCR repertoires and distinct mechanisms to carry out γδ T cell responses. The γδTCRs expressed on their cellular surfaces can detect and bind antigens in an MHC-unrestricted manner, rendering γδ T cells functionally independent of antigen-presenting cells (macrophages, B cells, dendritic cells), an appealing attribute for immunotherapeutic development and antitumor immunity [14].
Variations in the type of TCR Vδ chain of γδ T cells classify them into three major distinct populations, Vδ1, Vδ2, and Vδ3 [15]. The expression of the Vδ2 chain is most prevalent among circulating γδ T cells in human blood, with the Vδ2 identity accounting for 50–95% of peripheral blood γδ T cells and commonly paired with the Vγ9 chain, forming the Vγ9Vδ2 T cell subtype [15]. Vγ9Vδ2 T cells can be activated by phosphoantigens and pyrophosphates emerging from the mevalonate pathway of isoprenoid biosynthesis in eukaryotes [16,17].
Activated Vγ9Vδ2 cells can infiltrate the brain parenchyma in response to infection and are thus potent producers of immunostimulatory cytokines such as interferon-γ (IFN-γ) and tumor necrosis factor-α (TNF-α) [14]. These inflammatory cytokines have crucial functions in the immune antitumor response. IFN-γ is a potent activator of macrophages, dendritic cells, and cytotoxic T cells. It exerts antitumor cytotoxicity in tandem with perforin and granzyme and can enhance TNF-mediated apoptosis [18]. TNF-α is a cytokine involved in several signaling cascades that predominantly result in the induction of apoptosis in target cells, but it can also potentiate the activation of cytotoxic T cells [18]. The release of IFN-γ and TNF-α is associated with strong immunological antitumor responses and, as sources of these cytokines, γδ cells are thus important modulators of the immune response to cancer [19].
While there is no known native γδ T cell population in the brain parenchyma, the other two populations of γδ T cells, Vδ1 and Vδ3, typically reside in tissue at mucosal sites. Cells of these subtypes can be found patrolling or residing in the meninges and are involved in the homeostatic maintenance of the brain [20]. They have been shown to promote the response to immune checkpoint blockade in HLA-class-I-negative mismatch-repair-deficient cancers that have the genomic inactivation of β2-microglobulin [21]. γδ T cells execute functions of innate as well as adaptive immunity, since they feature clonally rearranged TCR genes, but do not require antigen presentation or processing to exert effector functions [22].
3. Antitumor Activity of γδ T Cells in GBM
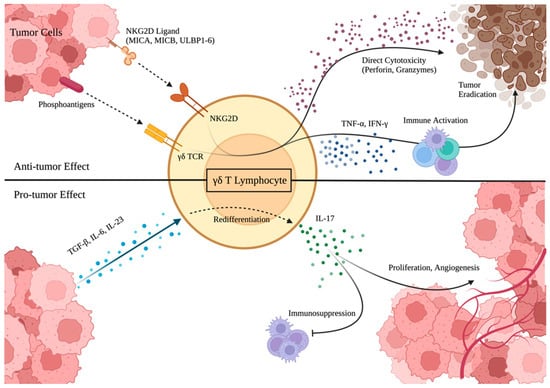
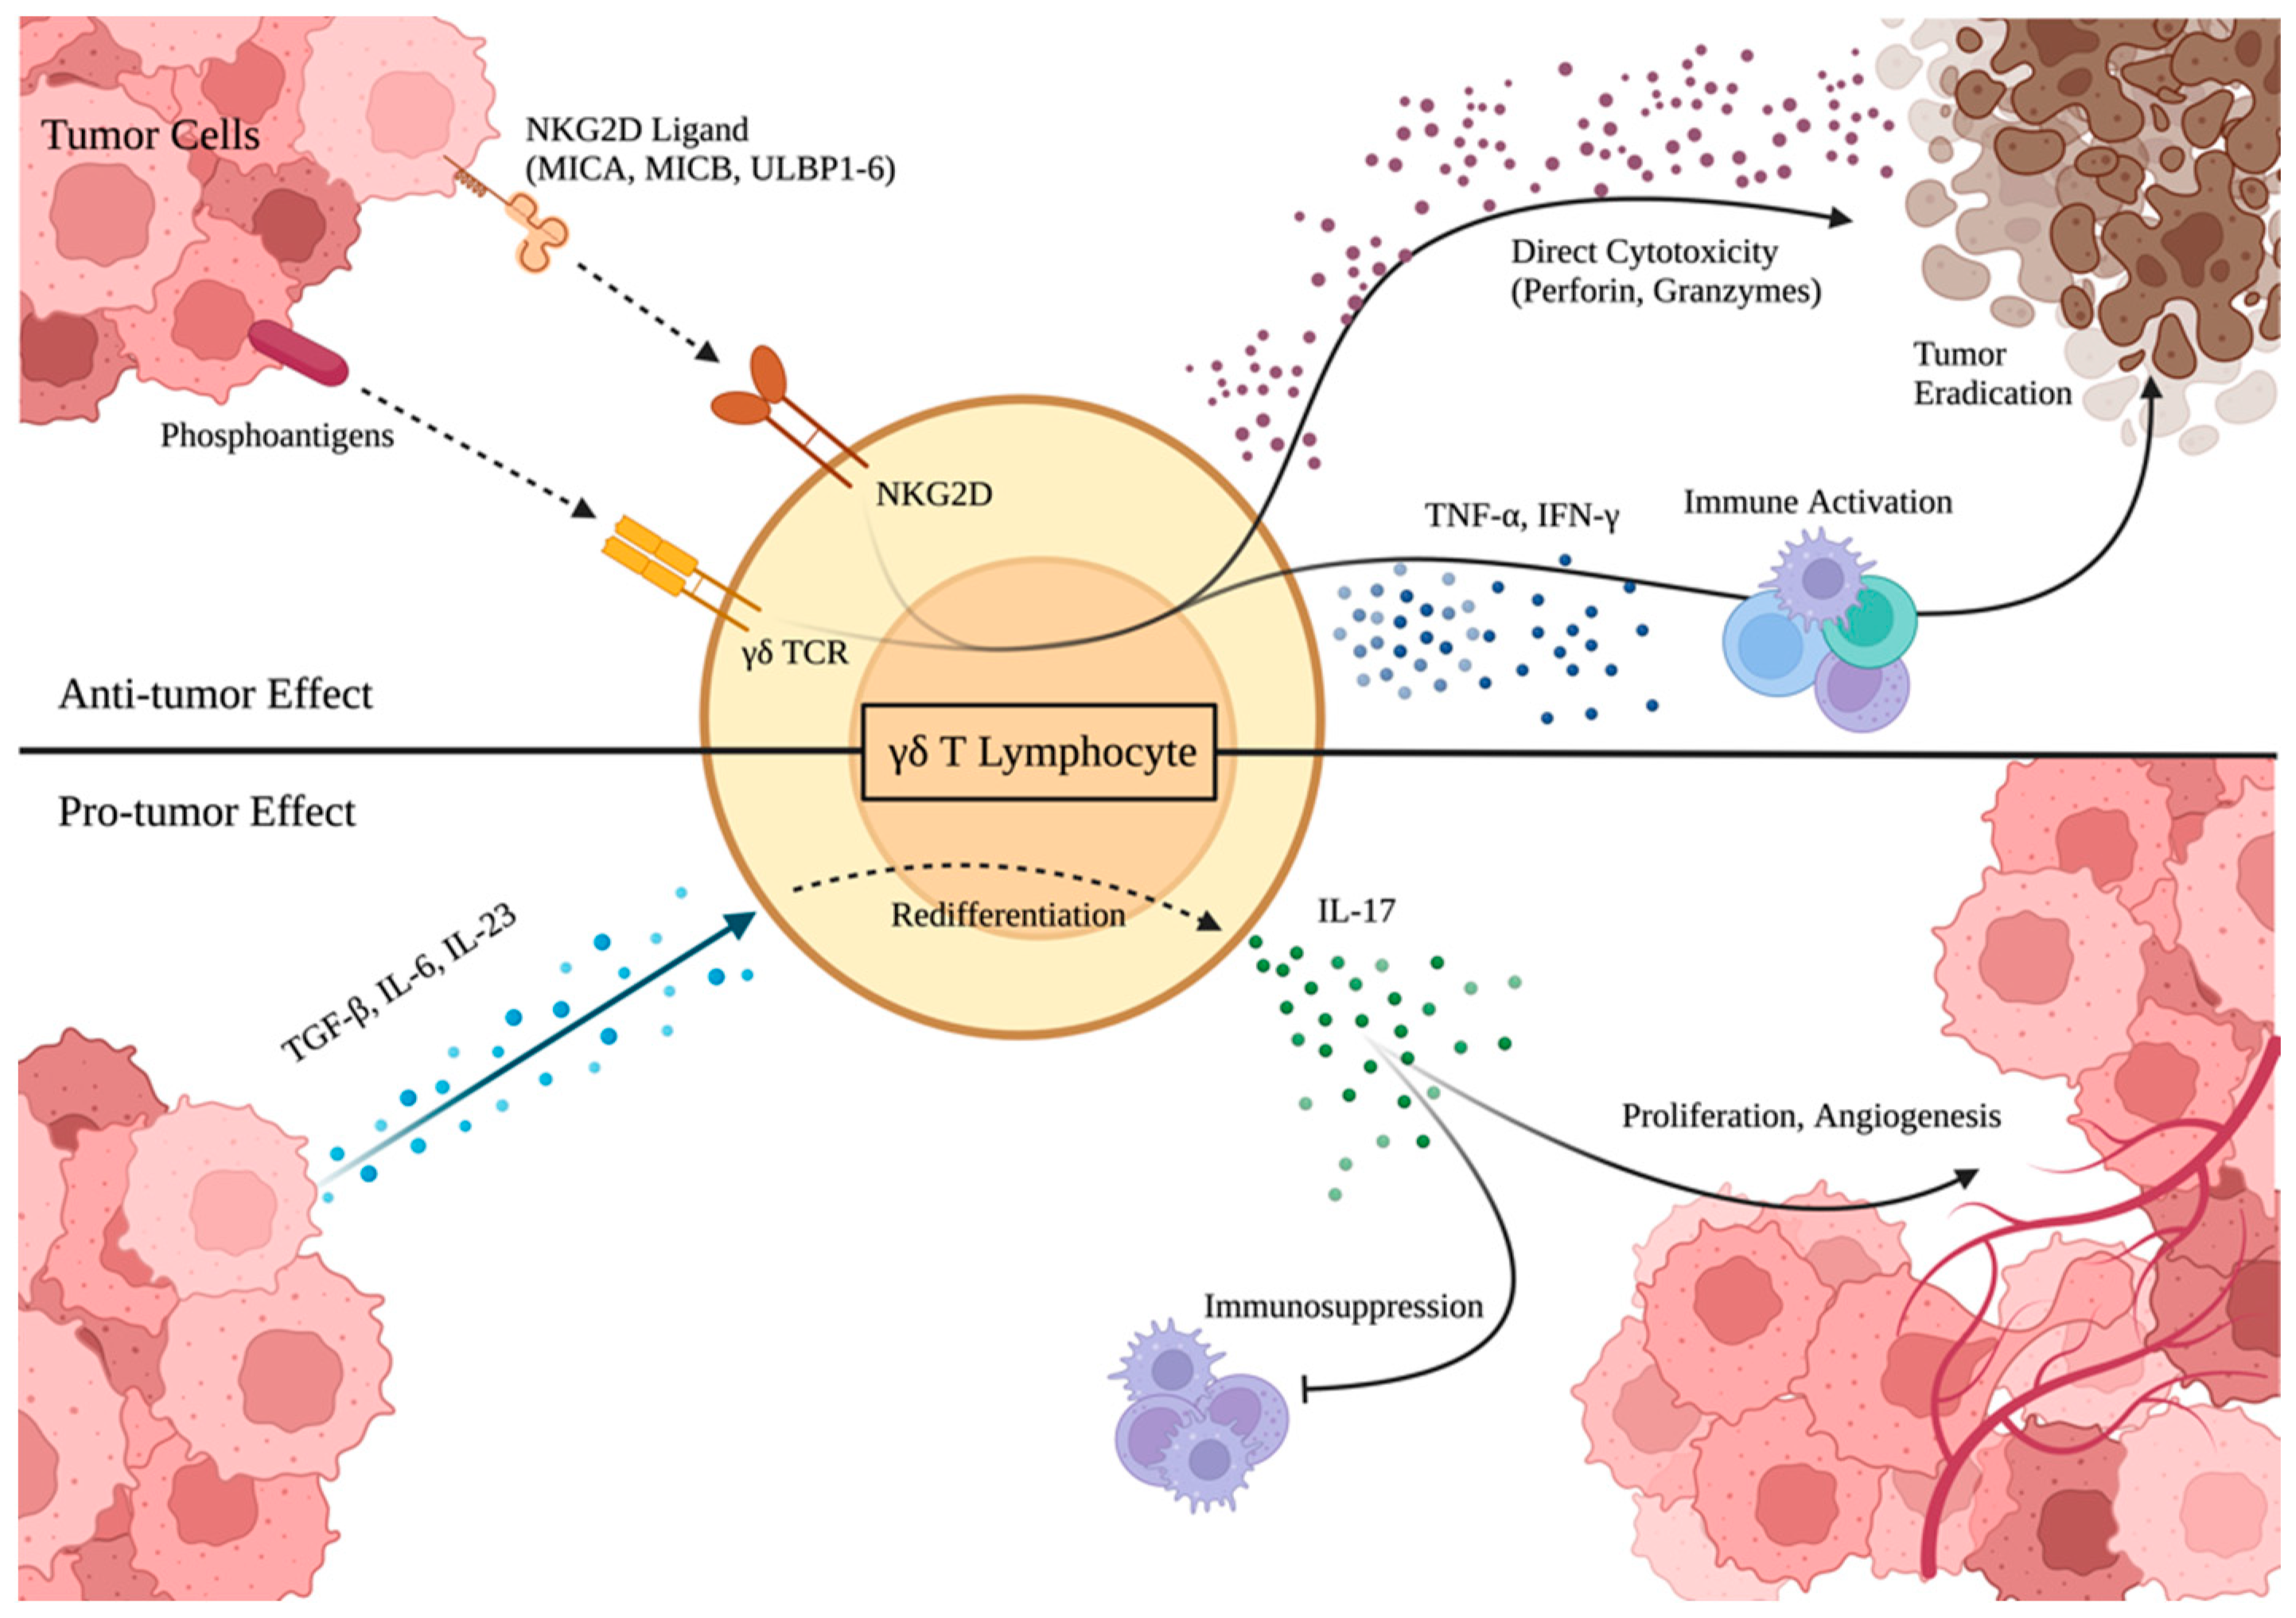
γδ T cells have demonstrated promising potential as effective immunotherapeutic agents against a variety of brain cancers, including GBM (Table 1). This reactivity is associated with TCR-mediated cytotoxicity coupled with the constitutive expression of natural killer (NK) cell receptors, like NKG2D, on γδ T cells [23,24]. Gliomas express detectable concentrations of ligands that are recognized by the γδ TCR and NKG2D receptors present on γδ T cells [25] (Figure 2). Eight NKG2D ligands (NKG2DL), all found in GBM, are known: two from the group of MHC class I chain-related proteins, MICA and MICB, and six from the UL16-binding protein family, ULBP1-6 [26,27]. One study demonstrated that γδ T cells exposed to mitogen, an NKG2DL, developed lytic activity against both GBM cell lines and patient-derived explants in vitro [28]. Indeed, the increased presence of NKG2DL among in vitro GBM cell lines treated with Temozolomide (TMZ) was linked with increased γδ T cell lysis of the GBM cells when in co-culture, indicating that the expression of NKG2D in γδ T cells contributes to their ability to recognize and lyse tumor cells [24].
Table 1.
Overview of relevant γδ T cell studies in GBM (n = 15). [8,13,23,24,28,29,30,31,32,33,34,35,36,37,38].
Figure 2.
Illustration of antitumor and protumor effects of infiltrating γδ T cells. Infiltrating γδ T cells are thought to display great plasticity and to be heavily influenced by their environment. NKG2D ligands and phosphoantigens in the GBM tumor microenvironment engage with the NKG2D receptor and γδ TCR, respectively (dotted arrows). Antitumor γδ T cells exhibit direct cytotoxicity through the release of perforin and granzymes, which lyse tumor cells. Alternatively, the release of several cytokines (IFN-γ, TNF-α) results in the immune activation of several tumor-infiltrating leukocytes, including NK cells, macrophages, and other T cells. However, the presence of a significant concentration of TGF-β, IL-6, and IL-23 can induce IL-17 production from infiltrating γδ T cells, resulting in protumor activity. IL-17 can directly promote angiogenesis and tumor migration and proliferation while also facilitating an immunosuppressive signal cascade. Created with BioRender.com and published with permission.
An important aspect of γδ T cell reactivity towards tumors is the conservation of NKG2D expression among the various subtypes of γδ T cells [23]. Vγ9Vδ2 T cells, expressing NKG2D, can potentially eradicate NKG2DL-presenting GBM cells and, more specifically, mesenchymal GBM cells [39]. In an in vitro study of human primary GBM cultures, γδ T cells were shown to be activated by exposure to GBM and even polarized towards a strong antitumor identity when exposed to the GBM culture supernatant [23]. When co-cultured with human primary GBM cells, such antitumor activity was characterized by the increased production of cytokines, particularly of intracellular perforin, IFN-γ, and TNF-α [37]. This demonstrated the ability of γδ T cells to identify and attack GBM cells. This reactivity towards GBM tumors has been shown to be resilient and effective both naturally and when implemented through adoptive transfer therapies. In murine models, following adoptive transfer, allogeneic human Vγ9Vδ2 T cells were able to survive and pervade within the brain parenchyma for several days and successfully eradicated infiltrative orthotopic primary human GBM cells [8]. Allogenic γδ T cells, when stimulated in vitro and transferred to a murine host, maintained the ability to target and eliminate the human primary GBM cells of the host [35]. Overall, the most effective method of using the natural properties of γδ T cells has been adoptive cell therapy. However, new avenues of γδ T cell therapy have focused on sensitizing γδ T cells to GBM and enhancing their cytotoxicity to specific cancer cell lines.
4. Phosphoantigen Stimulation and Combined Therapies
To achieve greater efficacy for clinical use, the natural reactivity of γδ T cells can be enhanced through stimulation with phosphoantigens. Other approaches have also investigated the possible synergistic effect of TMZ in enhancing the targeting of GBM. In in vivo GBM xenografts, the intraperitoneal administration of minodronate, a nitrogen-containing bisphosphonate, induced antitumor effects on GBM tumors and acted synergistically with γδ T cells [34]. Stimulation with the phosphoantigen (E)-4-hydroxy-3-methyl-but-2-enyl pyrophosphate (HMBPP) contributed to γδ T cell differentiation into a T helper 1 (Th1)-like profile when cultured with primary GBM cultures or derived medium [37]. The Th1 profile has been known to have an antitumor response and is associated with the increased production of IFN-γ and TNF-α. In fact, a reliable indicator of the successful response of γδ T cells is IFN-γ expression [19]. Many experiments thus use IFN-γ as an indicator of the magnitude of activity. The finding that phosphoantigen stimulation induced the adoption of a Th1-like profile by γδ T cells alludes to the potential of building larger-scale immune responses towards GBM cells [37]. Additionally, though phosphoantigen stimulation is commonly used to prepare γδ T cells for adoptive transfer therapy, the cytotoxicity induced by lymphocytes can further be enhanced by combining them with chemotherapy or radiation. Studies have demonstrated that TMZ increases NKG2D ligands on GBM cells, increasing their susceptibility to γδ T-cell-mediated clearance [24,25,31]. To overcome the toxic effects of TMZ, Lamb et al. genetically engineered γδ T cells to resist TMZ toxicity by inserting an MGMT transgene, producing the DNA repair enzyme O(6)-alkyguanine DNA alkyltransferase (AGT) [31]. This alteration did not affect the potency of the γδ T cell killing of GBM cells; rather, the TMZ-resistant lymphocytes offered a combinatorial approach to merging chemotherapy with γδ T cell immunotherapy. Additionally, other in vitro investigations have shown that allogeneic human Vγ9Vδ2 T cells exert cytotoxic effects on and spontaneously eliminate GBM cells with a mesenchymal signature. In particular, γδ T cells activated with zoledronate and IL-2 were shown to significantly eradicate cells from three GBM cell lines (U87MG, U138MG, and A172) [32]. Finally, since NKG2D was found to be an integral part of the anti-GBM-induced cytotoxicity by γδ T cells, increasing the GBM cell expression of NKG2DLs would have the effect of further inciting the γδ T cell lysis of tumor cells. Indeed, treating glioma cells with TMZ and/or radiation resulted in the increased surface expression of NKG2DL, which sensitized the GBM cells to cell killing by γδ T cells and precipitated a greater degree of γδ T-cell-induced lysis of GBM cells [26]. In NKG2D-intact mice, γδ T cells produced more IFN-γ upon treatment with TMZ, proving that TMZ treatment facilitated enhanced Vγ9Vδ2 T-cell-mediated GBM cell killing [24].
5. Challenges to Clinical Use
Despite its promising potential, there are existing challenges facing the clinical use of γδ T cells in cell-based therapies. First, since γδ T cells account for a minor population of T lymphocytes and there are differences in the cells between humans and mice, translating the results from one species to another is challenging. Though mice and human γδ T cells share several characteristics, evolutionary divergences, especially in the γδ TCR, make direct comparisons difficult [40]. The attested γδ T cell antitumor activity in mice should not be assumed to be retained in humans. Several publications report on the efficacy of human γδ T cells specifically in GBM, a summary of which can be found in Table 1. However, more investigations of human γδ T cells’ anti-GBM properties are necessary to corroborate any murine-based findings [41].
Second, most clinical trials of cancer treatment with γδ T cells have used the Vδ2+ type, particularly the Vγ9Vδ2 subset, due to their higher abundance relative to other types, leaving the Vδ1 and Vδ3 chains under-investigated [41]. However, since γδ T cells comprise only 1–5% of the T cells in human peripheral blood and the Vγ9Vδ2 subset represent only 5–10% of CD3+ type cells, harvesting and expanding γδ T cells cost-efficiently is difficult [42]. Traditionally, γδ T cells are harvested from the population of peripheral blood mononuclear cells (PBMCs) using the Ficoll-Paque separation method. Once harvested, they go through multiple technically challenging isolations for purification from other immune cells, particularly NK cells [43]. While no standard method of γδ T cell isolation and expansion prevails, immunomagnetic cell separation is also commonly used. Prior studies have shown that they can be expanded after isolation [43]. However, the harvesting and purification of γδ T cells remains the most significant technical hurdle for their clinical use [44,45].
Finally, the potential protumor properties of γδ T cells present a clear challenge to their therapeutic use. For example, studies have shown that γδ T cells suppress antitumor immune responses in breast cancer and are linked to poor survival in colorectal, breast, and gallbladder cancer [46,47,48]. Studies in brain tumors present contradictory findings, with protumor and antitumor activity both evidenced in different conditions.
6. Protumor Activity of γδ T Cells
The potential for protumor activity by certain subtypes of γδ T cells stands as a significant caveat inherent to γδ T cell immunotherapy. While γδ T cells can successfully infiltrate tumors, differences in the composition of the TME may determine whether they execute a pro- or antitumor effect [19]. (Figure 2) If certain TME conditions are present, tumor-infiltrating γδ T cells will initiate a protumor response associated with interleukin-17 (IL-17) production [19]. As a cytokine ordinarily active in pro-inflammatory responses, IL-17 can be produced by CD4+ T cells, NK T cells, and γδ T cells [49]. IL-17 has a broad range of functions related to adaptive immunity and mediates several effector cytokine cascades in the immune response to bacterial, fungal, and parasitic pathogens, particularly within mucosal barriers [49]. It has a key role in neutrophil recruitment as well as the direct neutrophil- and macrophage-mediated killing of pathogens and is a prominent potentiator of the inflammatory response [50]. However, the chronic inflammation linked to IL-17 has been shown to exert a pro-tumorigenic effect and contributes to immunosuppression within the TME [47]. In several cancers, IL-17 has been indicted as an inducer of tumor angiogenesis and is generally associated with poor survival [46,48]. In the TME of GBM, some studies indicate that the γδ T cell production of IL-17 can promote tumor growth and survival [19,51].
Within tumors, the emergence of the IL-17 production phenotype is linked to the tumor necrosis factor receptor (TNFR) CD27. CD27+ γδ T cells respond to ligands by producing IFN-γ, which is associated with an antitumor effect, whereas CD27− γδ T cells may be responsible for IL-17 production [52]. While this quality is useful for adaptive immune responses, in the context of the TME, it can result in the rapid production of IL-17 and a potential protumor effect. The primary source of protumor IL-17 production within TMEs has not been previously established, but there is evidence that γδ T cells play a role in this phenotype [52].
The mechanism of inducing CD27− γδ T cell populations into producing IL-17 involves the engagement of certain ligands of γδTCR and NKG2D and cytokines in the TME, such as IL-1β, IL-6, IL-23, and TGF-β [53,54]. As a pleiotropic cytokine, TGF-β has several immune-related functions, including both pro- and anti-inflammatory effects. It is commonly produced by cancer cells and, in the context of the TME, promotes angiogenesis and facilitates immunosuppression through driving the differentiation of regulatory T cells [55]. TGF-β is also implicated in driving γδ T cells towards IL-17 production, acting concertedly with IL-6 to induce an IL-17-producing identity [56,57]. The pro-inflammatory cytokines IL-1β and IL-23 have major roles in autoimmunity and are key to the development of Th17 cells, which innately produce IL-17, from naïve T cells in response to viral and microbial infection [58]. Studies have shown that IL-23 in combination with IL-1β can induce the constitutive expression of IL-17 in γδ T cells directly or promote their expansion in tandem with TGF-β [57,58]. Thus, it is likely that a combination of these cytokine signals in the TME drives γδ T cells towards IL-17 production and brings about the protumor effect. Although understudied, if γδ T cell IL-17 production persists within GBM, it would be critical to further investigate the specific role of IL-17 in the GBM TME.
Within GBMs, the role of IL-17 has not been thoroughly investigated, with sparse evidence supporting both its pro- and antitumor effects. Some studies have correlated IL-17 production in GBM with enhanced tumor metastasis. Zheng et al. found that U251 and U87MG GBM cells exposed to exogenous IL-17A in vitro exhibited increased aggression and a greater capacity for migration and invasion [59]. The presence of IL-17 increased GBM cell survival and proliferation through PI3K/Akt pathway activation, which is a major regulator of cell survival, migration, and invasion [59]. However, there have been findings that contradict the notion of a universal protumor effect of IL-17 in GBM. In an assessment of GBM tissue resected from 41 patients, increased IL-17 expression was associated with a more favorable prognosis. Patients who had elevated levels of IL-17 expressed in tumors had significantly longer survival than patients with low IL-17 [51]. The correlation between higher IL-17 production and increased survival was consistent with some studies in other cancers, such as ovarian and small cell lung cancers, while others maintained the role of IL-17 as a negative prognostic indicator [60,61,62]. Thus, additional studies are needed to elucidate which conditions render IL-17 a pro- or antitumor agent in GBM.
7. Effect of TME Hypoxia on γδ T Cells
A characteristic feature of GBMs is their immunosuppressive TME, consisting of inhibitory regulators of the immune response and overall hypoxic conditions [63]. Hypoxia is prevalent in many solid malignant tumors and especially in GBM, where vessel occlusion and dysfunctional vascularization lead to significantly reduced oxygen levels from the physiological tissue conditions of 2–9% O2 [63,64]. A 2002 study investigating changes in oxygenation within GBMs recorded intratumoral oxygen levels as low as 1.25% and 1.0% O2 while awake and asleep, respectively [65]. Such low O2 levels within the TME allow for the recruitment of immunosuppressive tumor-associated macrophages (TAMs) and regulatory T cells, which, in hypoxic conditions, suppress T cell responses and negatively regulate their function [66].
Oxygen-poor TMEs have been known to inhibit the effectiveness of immune cells, a characteristic observed in γδ T cells [67,68]. The few studies examining the effect of TME hypoxia on γδ T cells have shown that such hypoxia-induced immunosuppression is conserved among them. In vitro studies on oral tumor and breast cancer cell lines showed the diminished cytotoxic capability of γδ T cells in hypoxic conditions [68,69]. One GBM-centered study also investigated the effect of hypoxia on γδ T cells. Park et al. examined the cytotoxicity of γδ T cells in vivo and in vitro under hypoxic conditions in a GL261 orthotopic high-grade glioma (HGG) murine model. They discovered that hypoxia was associated with decreased expression of NKG2D in γδ T cells, an increased presence of hypoxia-inducible factor 1-α (HIF1α), and decreased overall cytotoxic activity. Conversely, when hypoxia was alleviated through the administration of metformin and inhibition of HIF1α, NKG2D expression was enhanced, and the antitumor response returned [36]. These results indicate that hypoxia may inhibit the antitumor effect of γδ T cells in GBM by driving a reduction in the expression of NKG2D as one of the mechanisms [36]. Additionally, some studies have linked the activation of HIF1α with IL-17 production related to inflammatory immune responses, indicating that tumor hypoxia may contribute to IL-17 production and the associated protumor effect [70]. However, the relationship between HIF1α and IL-17 has not been extensively examined, and thus no definitive conclusion can be drawn. These findings represent only a few studies examining the relationship of γδ T cell cytotoxicity and hypoxia in GBM. The mechanistic influence of hypoxia on γδ T cells is a critical avenue to investigate in future studies.
8. Future Directions
The efficacy of γδ T cells against GBM gives them potential as an immunotherapeutic approach. Their MHC independence and the presence of combined NKG2D and γδ TCR-facilitated tumor recognition endows the γδ T cells with natural antitumor effects and the potential to overcome key immune evasion mechanisms of GBM [14,24]. Such qualities can be harnessed and amplified through phosphoantigen stimulation and combined with chemotherapy approaches, making for an attractive clinical application [37,38]. However, several gaps in our understanding must be filled before γδ T cells can be used as immunotherapeutic agents in GBM. First, the risk of a protumor effect stands as a fundamental caveat for γδ T cell immunotherapy that requires further exploration (Figure 2). The relatively few studies conducted on IL-17 in γδ T cells and its association with different outcomes are contradictory, with studies reporting both pro- and antitumor effects [51,59]. It is likely that different TME conditions influence the protumor potential of γδ T cells [19]. Therefore, additional studies analyzing γδ T cells in co-culture with GBM will further elucidate the pathology of the protumor phenotype. It is also particularly important for in vivo studies to investigate the conditions and TME components, including hypoxia, that may polarize γδ T cells towards a protumor identity [60,70]. Understanding the main players influencing the protumor potential of γδ T cells is necessary to ensure optimal safety for clinical usage. Further, due to the differences between γδ T cells in humans and mice, any results found in murine models must be replicated in humans [40].
Beyond in vivo and in vitro studies, clinical investigations are warranted to clarify the role of γδ T cells within GBM patients. γδ T cell infiltration of many cancer types, including GBM, generally confers a positive prognosis [19,71]. There is also evidence, however, that in progressed tumor conditions, their presence can be a negative survival indicator [19]. This question could be answered by harvesting pathological tissue, performing single-cell RNA sequencing to identify γδ T cells, and identifying the relationship between survival and the magnitude of γδ T cell activity. Large-scale databases, such as the TCGA, may also be useful resources for studying the clinical impact of γδ T cell infiltration retrospectively.
The final barriers to the clinical use of γδ T cells are harvesting, purifying, and expanding the cells. The low population of γδ T cells in the blood and the difficulty of purifying them from other lymphocytes make the process cost-inefficient for production at the scale necessary for clinical implementation [42,43,44,45]. The refinement of existing techniques or the discovery of new ones could help to alleviate this limitation. Once the production of γδ T cells is more cost-efficient, then they could be reliably used in GBM immunotherapy research.
9. Conclusions
With γδ T cells’ unique ability to recognize antigens independent of MHCs and infiltrate tumors, they have incredible potential to serve as a new treatment strategy for patients with a variety of cancers, especially GBM. In this review, we presented an overview of the biology of γδ T cells, as well as discussing the existing challenges to their clinical use. We described the mechanisms of their potential pro- and antitumor effects. We highlighted several key remaining questions and the potential research projects to address them. Ultimately, remedying these shortcomings in our knowledge of γδ T cells and their immunotherapeutic potential will pave the way for their clinical use against GBM.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/cancers15245784/s1, Figure S1. Using the databases PubMed, ScienceDirect, and JSTOR, authors searched for published studies on γδ T cells over the period of 1995–2022. The searches were conducted using several terms comprised of combinations of the following: γδ T cells, glioblastoma, GBM, hypoxia, TME, phosphoantigens, IL-17, protumor, antitumor, infiltration, animal models, NKG2D, cytotoxicity, immunotherapy, preclinical models, and clinical trials. Publications were collected and sorted with emphasis put on the recency of studies as well as relevance to glioblastoma immunotherapy. Each article’s reference section was also searched to screen for additional studies. After collecting and reviewing an initial population of publications, subsequent searches were conducted to flesh out specific sections of the review, including the protumor effect, tumor microenvironment, and hypoxia sections. For example, when drafting the ‘Effect of TME Hypoxia on γδ T Cells’ section, the search terms inputted were γδ T cells:TME:hypoxia, and/or γδ T cells:hypoxia.
Author Contributions
Conceptualization, T.A., H.K., T.D.A., and J.R.-T.; methodology, T.A., H.K., and J.R.-T.; writing—original draft preparation, T.A., H.K., C.W.-L., and J.R.-T.; writing—review and editing, T.A., H.K., C.W.-L., T.D.A., C.M.J., K.G., C.B., and J.R.-T. All authors have read and agreed to the published version of the manuscript.
Funding
J.R.T. is an NINDS R25 training grant awardee (5R25NS065729).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created in this review.
Conflicts of Interest
C.B. is a consultant for Depuy-Synthes and Bionaut Labs. C.M.J. is a consultant and shareholder of Egret Therapeutics. He receives research support from In Cephalo. The remaining authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest.
References
- Stupp, R.; Mason, W.P.; van den Bent, M.J.; Weller, M.; Fisher, B.; Taphoorn, M.J.B.; Belanger, K.; Brandes, A.A.; Marosi, C.; Bogdahn, U.; et al. Radiotherapy plus Concomitant and Adjuvant Temozolomide for Glioblastoma. Available online: https://www.nejm.org/ (accessed on 1 October 2023).
- Stupp, R.; Taillibert, S.; Kanner, A.; Read, W.; Steinberg, D.M.; Lhermitte, B.; Toms, S.; Idbaih, A.; Ahluwalia, M.S.; Fink, K.; et al. Effect of tumor-treating fields plus maintenance temozolomide vs maintenance temozolomide alone on survival in patients with glioblastoma a randomized clinical trial. JAMA J. Am. Med. Assoc. 2017, 318, 2306–2316. [Google Scholar] [CrossRef] [Scilit]
- Almeida, J.P.; Chaichana, K.L.; Rincon-Torroella, J.; Quinones-Hinojosa, A. The Value of Extent of Resection of Glioblastomas: Clinical Evidence and Current Approach. Curr. Neurol. Neurosci. Rep. 2015, 15, 517. [Google Scholar] [CrossRef] [Scilit]
- Pearson, J.R.D.; Cuzzubbo, S.; McArthur, S.; Durrant, L.G.; Adhikaree, J.; Tinsley, C.J.; Pockley, A.G.; McArdle, S.E.B. Immune Escape in Glioblastoma Multiforme and the Adaptation of Immunotherapies for Treatment. Front. Immunol. 2020, 11, 582106. [Google Scholar] [CrossRef] [Scilit]
- Scharping, N.E.; Delgoffe, G.M. Tumor microenvironment metabolism: A new checkpoint for anti-tumor immunity. Vaccines 2016, 4, 46. [Google Scholar] [CrossRef] [Scilit]
- Pombo Antunes, A.R.; Scheyltjens, I.; Duerinck, J.; Neyns, B.; Movahedi, K.; Van Ginderachter, J.A. Understanding the glioblastoma immune microenvironment as basis for the development of new immunotherapeutic strategies. Elife 2020, 9, e52176. [Google Scholar] [CrossRef] [Scilit]
- Godfrey, D.I.; Le Nours, J.; Andrews, D.M.; Uldrich, A.P.; Rossjohn, J. Unconventional T Cell Targets for Cancer Immunotherapy. Immunity 2018, 48, 453–473. [Google Scholar] [CrossRef] [Scilit]
- Jarry, U.; Chauvin, C.; Joalland, N.; Léger, A.; Minault, S.; Robard, M.; Bonneville, M.; Oliver, L.; Vallette, F.M.; Vié, H.; et al. Stereotaxic administrations of allogeneic human Vγ9Vδ2 T cells efficiently control the development of human glioblastoma brain tumors. Oncoimmunology 2016, 5, e1168554. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, Z.; Hambardzumyan, D. Immune microenvironment in glioblastoma subtypes. Front. Immunol. 2018, 9, 1004. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee-Chang, C.; Rashidi, A.; Miska, J.; Zhang, P.; Pituch, K.C.; Hou, D.; Xiao, T.; Fischietti, M.; Kang, S.J.; Appin, C.L.; et al. Myeloid-derived suppressive cells promote B cell-mediated immunosuppression via transfer of PD-L1 in glioblastoma. Cancer Immunol. Res. 2019, 7, 1928–1943. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martinez-Lage, M.; Lynch, T.M.; Bi, Y.; Cocito, C.; Way, G.P.; Pal, S.; Haller, J.; Yan, R.E.; Ziober, A.; Nguyen, A.; et al. Immune landscapes associated with different glioblastoma molecular subtypes. Acta Neuropathol. Commun. 2019, 7, 203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, S.; Song, Z.; Zhang, T.; He, X.; Huang, K.; Zhang, Q.; Shen, J.; Pan, J. Identification of Immune Cell Infiltration and Immune-Related Genes in the Tumor Microenvironment of Glioblastomas. Front. Immunol. 2020, 11, 585034. [Google Scholar] [CrossRef] [Scilit]
- Lee, M.; Park, C.; Woo, J.; Kim, J.; Kho, I.; Nam, D.-H.; Park, W.-Y.; Kim, Y.-S.; Kong, D.-S.; Lee, H.W.; et al. Preferential Infiltration of Unique Vγ9Jγ2-Vδ2 T Cells Into Glioblastoma Multiforme. Front. Immunol. 2019, 10, 555. [Google Scholar] [CrossRef] [Scilit]
- Willcox, C.R.; Mohammed, F.; Willcox, B.E. The distinct MHC-unrestricted immunobiology of innate-like and adaptive-like human γδ T cell subsets—Nature’s CAR-T cells. Immunol. Rev. Vol. 2020, 298, 25–46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kabelitz, D.; Kalyan, S.; Oberg, H.-H.; Wesch, D. Human Vδ2 versus non-Vδ2 γδ T cells in antitumor immunity. Oncoimmunology 2013, 2, e23304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tanaka, Y.; Morita, C.T.; Tanaka, Y.; Nieves, E.; Brenner, M.B.; Bloom, B.R. Natural and synthetic non-peptide antigens recognized by human γδ T cells. Nature 1995, 375, 155–158. [Google Scholar] [CrossRef] [Scilit]
- Yuan, L.; Ma, X.; Yang, Y.; Qu, Y.; Zhu, X.; Ma, W.; Duan, J.; Xue, J.; Yang, H.; Huang, J.-W.; et al. Phosphoantigens glue butyrophilin 3A1 and 2A1 to activate Vγ9Vδ2 T cells. Nature 2023, 621, 840–848. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jorgovanovic, D.; Song, M.; Wang, L.; Zhang, Y. Roles of IFN-γ in tumor progression and regression: A review. Biomark. Res. 2020, 8, 49. [Google Scholar] [CrossRef] [Scilit]
- Presti, E.L.; Toia, F.; Oieni, S.; Buccheri, S.; Turdo, A.; Mangiapane, L.R.; Campisi, G.; Caputo, V.; Todaro, M.; Stassi, G.; et al. Squamous cell tumors recruit γδ T cells producing either IL17 or IFNγ depending on the tumor stage. Cancer Immunol. Res. 2017, 5, 397–407. [Google Scholar] [CrossRef] [Scilit]
- de Lima, K.A.; Rustenhoven, J.; Da Mesquita, S.; Wall, M.; Salvador, A.F.; Smirnov, I.; Cebinelli, G.M.; Mamuladze, T.; Baker, W.; Papadopoulos, Z.; et al. Meningeal γδ T cells regulate anxiety-like behavior via IL-17a signaling in neurons. Nat. Immunol. 2020, 21, 1421–1429. [Google Scholar] [CrossRef] [Scilit]
- de Vries, N.L.; van de Haar, J.; Veninga, V.; Chalabi, M.; Ijsselsteijn, M.E.; van der Ploeg, M.; Bulk, J.v.D.; Ruano, D.; Berg, J.G.v.D.; Haanen, J.B.; et al. γδ T cells are effectors of immunotherapy in cancers with HLA class I defects. Nature 2023, 613, 743–750. [Google Scholar] [CrossRef] [Scilit]
- Kabelitz, D.; Serrano, R.; Kouakanou, L.; Peters, C.; Kalyan, S. Cancer immunotherapy with γδ T cells: Many paths ahead of us. Cell Mol. Immunol. 2020, 17, 925–939. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chauvin, C.; Joalland, N.; Perroteau, J.; Jarry, U.; Lafrance, L.; Willem, C.; Retière, C.; Oliver, L.; Gratas, C.; Gautreau-Rolland, L.; et al. NKG2D Controls Natural Reactivity of Vγ9Vδ2 T Lymphocytes against Mesenchymal Glioblastoma Cells. Clin. Cancer Res. 2019, 25, 7218–7228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chitadze, G.; Lettau, M.; Luecke, S.; Wang, T.; Janssen, O.; Fürst, D.; Mytilineos, J.; Wesch, D.; Oberg, H.-H.; Held-Feindt, J.; et al. NKG2D- and T-cell receptor-dependent lysis of malignant glioma cell lines by human γδ T cells: Modulation by temozolomide and A disintegrin and metalloproteases 10 and 17 inhibitors. Oncoimmunology 2016, 5, e1093276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiss, T.; Schneider, H.; Silginer, M.; Steinle, A.; Pruschy, M.; Polić, B.; Weller, M.; Roth, P. NKG2D-Dependent Antitumor Effects of Chemotherapy and Radiotherapy against Glioblastoma. Clin. Cancer Res. 2018, 24, 882–895. [Google Scholar] [CrossRef] [Scilit]
- Flüh, C.; Chitadze, G.; Adamski, V.; Hattermann, K.; Synowitz, M.; Kabelitz, D.; Held-Feindt, J. NKG2D ligands in glioma stem-like cells: Expression in situ and in vitro. Histochem. Cell Biol. 2018, 149, 219–233. [Google Scholar] [CrossRef] [Scilit]
- Raulet, D.H.; Gasser, S.; Gowen, B.G.; Deng, W.; Jung, H. Regulation of ligands for the NKG2D activating receptor. Annu. Rev. Immunol. 2013, 31, 413–441. [Google Scholar] [CrossRef] [Scilit]
- Bryant, N.L.; Suarez-Cuervo, C.; Gillespie, G.Y.; Markert, J.M.; Nabors, L.B.; Meleth, S.; Lopez, R.D.; Lamb, L.S., Jr. Characterization and immunotherapeutic potential of γδ T-cells in patients with glioblastoma. Neuro. Oncol. 2009, 11, 357–367. [Google Scholar] [CrossRef] [Scilit]
- Bryant, N.L.; Gillespie, G.Y.; Lopez, R.D.; Markert, J.M.; Cloud, G.A.; Langford, C.P.; Arnouk, H.; Su, Y.; Haines, H.L.; Suarez-Cuervo, C.; et al. Preclinical evaluation of ex vivo expanded/activated γδ T cells for immunotherapy of glioblastoma multiforme. J. Neurooncol. 2011, 101, 179–188. [Google Scholar] [CrossRef] [Scilit]
- Cimini, E.; Piacentini, P.; Sacchi, A.; Gioia, C.; Leone, S.; Lauro, G.; Martini, F.; Agrati, C. Zoledronic Acid Enhances Vδ2 T-Lymphocyte Antitumor Response to Human Glioma Cell Lines. Int. J. Immunopathol. Pharmacol. 2011, 24, 139–148. [Google Scholar] [CrossRef] [Scilit]
- Lamb, L.S., Jr.; Bowersock, J.; Dasgupta, A.; Gillespie, G.Y.; Su, Y.; Johnson, A.; Spencer, H.T. Engineered Drug Resistant γδ T Cells Kill Glioblastoma Cell Lines during a Chemotherapy Challenge: A Strategy for Combining Chemo- and Immunotherapy. PLoS ONE 2013, 8, e51805. [Google Scholar] [CrossRef] [Scilit]
- Nakazawa, T.; Nakamura, M.; Park, Y.S.; Motoyama, Y.; Hironaka, Y.; Nishimura, F.; Nakagawa, I.; Yamada, S.; Matsuda, R.; Tamura, K.; et al. Cytotoxic human peripheral blood-derived γδT cells kill glioblastoma cell lines: Implications for cell-based immunotherapy for patients with glioblastoma. J. Neuro-Oncology 2014, 116, 31–39. [Google Scholar] [CrossRef] [Scilit]
- Beck, B.H.; Kim, H.; O’brien, R.; Jadus, M.R.; Gillespie, G.Y.; Cloud, G.A.; Hoa, N.T.; Langford, C.P.; Lopez, R.D.; Harkins, L.E.; et al. Dynamics of Circulating γδ T Cell Activity in an Immunocompetent Mouse Model of High-Grade Glioma. PLoS ONE 2015, 10, e0122387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakazawa, T.; Nakamura, M.; Matsuda, R.; Nishimura, F.; Park, Y.S.; Motoyama, Y.; Hironaka, Y.; Nakagawa, I.; Yokota, H.; Yamada, S.; et al. Antitumor effects of minodronate, a third-generation nitrogen-containing bisphosphonate, in synergy with γδT cells in human glioblastoma in vitro and in vivo. J. Neurooncol. 2016, 129, 231–241. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joalland, N.; Chauvin, C.; Oliver, L.; Vallette, F.M.; Pecqueur, C.; Jarry, U.; Scotet, E. IL-21 Increases the Reactivity of Allogeneic Human Vγ9Vδ2 T Cells Against Primary Glioblastoma Tumors. J. Immunother. 2018, 41, 224–231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, J.H.; Kim, H.-J.; Kim, C.W.; Kim, H.C.; Jung, Y.; Lee, H.-S.; Lee, Y.; Ju, Y.S.; Oh, J.E.; Park, S.-H.; et al. Tumor hypoxia represses γδ T cell-mediated antitumor immunity against brain tumors. Nat. Immunol. 2021, 22, 336–346. [Google Scholar] [CrossRef] [Scilit]
- Rosso, D.A.; Rosato, M.; Iturrizaga, J.; González, N.; Shiromizu, C.M.; Keitelman, I.A.; Coronel, J.V.; Gómez, F.D.; Amaral, M.M.; Rabadan, A.T.; et al. Glioblastoma cells potentiate the induction of the Th1-like profile in phosphoantigen-stimulated γδ T lymphocytes. J. Neurooncol. 2021, 153, 403–415. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lamb, L.S.; Pereboeva, L.; Youngblood, S.; Gillespie, G.Y.; Nabors, L.B.; Markert, J.M.; Dasgupta, A.; Langford, C.; Spencer, H.T. A combined treatment regimen of MGMT-modified γδ T cells and temozolomide chemotherapy is effective against primary high grade gliomas. Sci. Rep. 2021, 11, 21133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Martinet, L.; Fleury-Cappellesso, S.; Gadelorge, M.; Dietrich, G.; Bourin, P.; Fournié, J.; Poupot, R. A regulatory cross-talk between Vγ9Vδ2 T lymphocytes and mesenchymal stem cells. Eur. J. Immunol. 2009, 39, 752–762. [Google Scholar] [CrossRef] [Scilit]
- Kazen, A.R.; Adams, E.J. Evolution of the V, D, and J gene segments used in the primate γδ T-cell receptor reveals a dichotomy of conservation and diversity. Proc. Natl. Acad. Sci. USA 2011, 108, E332–E340. [Google Scholar] [CrossRef] [Scilit]
- Silva-Santos, B.; Serre, K.; Norell, H. γδT cells in cancer. Nat. Rev. Immunol. 2015, 15, 683–691. [Google Scholar] [CrossRef] [Scilit]
- Presti, E.L.; Dieli, F.; Meraviglia, S. Tumor-infiltrating γδ T lymphocytes: Pathogenic role, clinical significance, and differential programing in the tumor microenvironment. Front. Immunol. 2014, 5, 607. [Google Scholar] [CrossRef] [Scilit]
- Makkouk, A.; Yang, X.; Barca, T.; Lucas, A.; Turkoz, M.; Wong, J.T.S.; Nishimoto, K.P.; Brodey, M.M.; Tabrizizad, M.; Gundurao, S.R.Y.; et al. Off-the-shelf Vδ 1 gamma delta T cells engineered with glypican-3 (GPC-3)-specific chimeric antigen receptor (CAR) and soluble IL-15 display robust antitumor efficacy against hepatocellular carcinoma. J. Immunother. Cancer 2021, 9, e003441. [Google Scholar] [CrossRef] [Scilit]
- Siegers, G.M.; Lamb, L.S. Cytotoxic and regulatory properties of circulating Vδ1+ γδ t cells: A new player on the cell therapy field? Mol. Ther. 2014, 22, 1416–1422. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nicol, A.J.; Tokuyama, H.; Mattarollo, S.R.; Hagi, T.; Suzuki, K.; Yokokawa, K.; Nieda, M. Clinical evaluation of autologous gamma delta T cell-based immunotherapy for metastatic solid tumours. Br. J. Cancer 2011, 105, 778–786. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, C.; Zhang, Q.; Ye, J.; Wang, F.; Zhang, Y.; Wevers, E.; Schwartz, T.; Hunborg, P.; Varvares, M.A.; Hoft, D.F.; et al. Tumor-Infiltrating γδ T Lymphocytes Predict Clinical Outcome in Human Breast Cancer. J. Immunol. 2012, 189, 5029–5036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, P.; Wu, D.; Ni, C.; Ye, J.; Chen, W.; Hu, G.; Wang, Z.; Wang, C.; Zhang, Z.; Xia, W.; et al. γδT17 Cells Promote the Accumulation and Expansion of Myeloid-Derived Suppressor Cells in Human Colorectal Cancer. Immunity 2014, 40, 785–800. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patil, R.S.; Shah, S.U.; Shrikhande, S.V.; Goel, M.; Dikshit, R.P.; Chiplunkar, S.V. IL17 producing γδT cells induce angiogenesis and are associated with poor survival in gallbladder cancer patients. Int. J. Cancer 2016, 139, 869–881. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weaver, C.T.; Hatton, R.D.; Mangan, P.R.; Harrington, L.E. IL-17 Family Cytokines and the Expanding Diversity of Effector T Cell Lineages. Annu. Rev. Immunol. 2007, 25, 821–852. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mills, K.H.G. IL-17 and IL-17-producing cells in protection versus pathology. Nat. Rev. Immunol. 2023, 23, 38–54. [Google Scholar] [CrossRef] [Scilit]
- Cui, X.; Xu, Z.; Zhao, Z.; Sui, D.; Ren, X.; Huang, Q.; Qin, J.; Hao, L.; Wang, Z.; Shen, L.; et al. Analysis of CD137l and IL-17 expression in tumor tissue as prognostic indicators for gliblastoma. Int. J. Biol. Sci. 2013, 9, 134–141. [Google Scholar] [CrossRef] [Scilit]
- Ribot, J.C.; Debarros, A.; Pang, D.J.; Neves, J.F.; Peperzak, V.; Roberts, S.J.; Girardi, M.; Borst, J.; Hayday, A.C.; Pennington, D.J.; et al. CD27 is a thymic determinant of the balance between interferon-γ- and interleukin 17-producing γδ T cell subsets. Nat. Immunol. 2009, 10, 427–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wakita, D.; Sumida, K.; Iwakura, Y.; Nishikawa, H.; Ohkuri, T.; Chamoto, K.; Kitamura, H.; Nishimura, T. Tumor-infiltrating IL-17-producing γδ T cells support the progression of tumor by promoting angiogenesis. Eur. J. Immunol. 2010, 40, 1927–1937. [Google Scholar] [CrossRef] [Scilit]
- Caccamo, N.; La Mendola, C.; Orlando, V.; Meraviglia, S.; Todaro, M.; Stassi, G.; Sireci, G.; Fournié, J.J.; Dieli, F. Differentiation, phenotype, and function of interleukin-17–producing human Vγ9Vδ2 T cells. Blood 2011, 118, 129–138. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prud’Homme, G.J. Pathobiology of transforming growth factor β in cancer, fibrosis and immunologic disease, and therapeutic considerations. Lab. Investig. 2007, 87, 1077–1091. [Google Scholar] [CrossRef] [Scilit]
- McGeachy, M.J.; Bak-Jensen, K.S.; Chen, Y.; Tato, C.M.; Blumenschein, W.; McClanahan, T.; Cua, D.J. TGF-β and IL-6 drive the production of IL-17 and IL-10 by T cells and restrain TH-17 cell–mediated pathology. Nat. Immunol. 2007, 8, 1390–1397. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sutton, C.E.; Lalor, S.J.; Sweeney, C.M.; Brereton, C.F.; Lavelle, E.C.; Mills, K.H. Interleukin-1 and IL-23 Induce Innate IL-17 Production from γδ T Cells, Amplifying Th17 Responses and Autoimmunity. Immunity 2009, 31, 331–341. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Beelen, A.J.; Zelinkova, Z.; Taanman-Kueter, E.W.; Muller, F.J.; Hommes, D.W.; Zaat, S.A.; Kapsenberg, M.L.; de Jong, E.C. Stimulation of the Intracellular Bacterial Sensor NOD2 Programs Dendritic Cells to Promote Interleukin-17 Production in Human Memory T Cells. Immunity 2007, 27, 660–669. [Google Scholar] [CrossRef] [Scilit]
- Zheng, Q.; Diao, S.; Wang, Q.; Zhu, C.; Sun, X.; Yin, B.; Zhang, X.; Meng, X.; Wang, B. IL-17A promotes cell migration and invasion of glioblastoma cells via activation of PI3K/AKT signalling pathway. J. Cell Mol. Med. 2019, 23, 357–369. [Google Scholar] [CrossRef] [Scilit]
- Kryczek, I.; Banerjee, M.; Cheng, P.; Vatan, L.; Szeliga, W.; Wei, S.; Huang, E.; Finlayson, E.; Simeone, D.; Welling, T.H.; et al. Phenotype, distribution, generation, and functional and clinical relevance of Th17 cells in the human tumor environments. Blood 2009, 114, 1141–1149. [Google Scholar] [CrossRef] [Scilit]
- Eruslanov, E.B.; Bhojnagarwala, P.S.; Quatromoni, J.G.; Stephen, T.L.; Ranganathan, A.; Deshpande, C.; Akimova, T.; Vachani, A.; Litzky, L.; Hancock, W.W.; et al. Tumor-associated neutrophils stimulate T cell responses in early-stage human lung cancer. J. Clin. Investig. 2014, 124, 5466–5480. [Google Scholar] [CrossRef] [Scilit]
- Gu, F.-M.; Gao, Q.; Shi, G.-M.; Zhang, X.; Wang, J.; Jiang, J.-H.; Wang, X.-Y.; Shi, Y.-H.; Ding, Z.-B.; Fan, J.; et al. Intratumoral IL-17+ Cells and Neutrophils show Strong Prognostic Significance in Intrahepatic Cholangiocarcinoma. Ann. Surg. Oncol. 2012, 19, 2506–2514. [Google Scholar] [CrossRef] [Scilit]
- Muz, B.; de la Puente, P.; Azab, F.; Azab, A.K. The role of hypoxia in cancer progression, angiogenesis, metastasis, and resistance to therapy. Hypoxia 2015, 3, 83–92. [Google Scholar] [CrossRef] [Scilit]
- Colwell, N.; Larion, M.; Giles, A.J.; Seldomridge, A.N.; Sizdahkhani, S.; Gilbert, M.R.; Park, D.M. Hypoxia in the glioblastoma microenvironment: Shaping the phenotype of cancer stem-like cells. Neuro Oncol. 2017, 19, 887–896. [Google Scholar] [CrossRef] [Scilit]
- Beppu, T.; Kamada, K.; Yoshida, Y.; Arai, H.; Ogasawara, K.; Ogawa, A. Change of oxygen pressure in glioblastoma tissue under various conditions. J. Neuro-Oncology 2002, 58, 47–52. [Google Scholar] [CrossRef] [Scilit]
- Henze, A.-T.; Mazzone, M. The impact of hypoxia on tumor-associated macrophages. J. Clin. Investig. 2016, 126, 3672–3679. [Google Scholar] [CrossRef] [Scilit]
- Ohta, A.; Diwanji, R.; Kini, R.; Subramanian, M.; Ohta, A.; Sitkovsky, M. In vivo T cell activation in lymphoid tissues is inhibited in the oxygen-poor microenvironment. Front. Immunol. 2011, 2, 27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sureshbabu, S.K.; Chaukar, D.; Chiplunkar, S.V. Hypoxia regulates the differentiation and anti-tumor effector functions of γδT cells in oral cancer. Clin. Exp. Immunol. 2020, 201, 40–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siegers, G.M.; Dutta, I.; Lai, R.; Postovit, L.-M. Functional plasticity of Gamma delta T cells and breast tumor targets in hypoxia. Front. Immunol. 2018, 9, 1367. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Konieczny, P.; Xing, Y.; Sidhu, I.; Subudhi, I.; Mansfield, K.P.; Hsieh, B.; Biancur, D.E.; Larsen, S.B.; Cammer, M.; Li, D.; et al. Interleukin-17 governs hypoxic adaptation of injured epithelium. Science 2022, 377, 170. [Google Scholar] [CrossRef] [Scilit]
- Gentles, A.J.; Newman, A.M.; Liu, C.L.; Bratman, S.V.; Feng, W.; Kim, D.; Nair, V.S.; Xu, Y.; Khuong, A.; Hoang, C.D.; et al. The prognostic landscape of genes and infiltrating immune cells across human cancers. Nat. Med. 2015, 21, 938–945. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).