


Abstract
Prolonged admission to the neonatal intensive care unit presents challenges for families, especially those displaced far from home. Understanding specific barriers to parental engagement in the NICU is key to addressing these challenges with hospital-based interventions. The objective of this qualitative study was to explore the impact of distance from home to hospital on the engagement of parents of very preterm infants (VPT) in the neonatal intensive care unit (NICU). We used a grounded theory approach and conducted 13 qualitative interviews with parents of VPT who were admitted ≥14 days and resided ≥50 miles away using a semi-structured interview guide informed by the socio-ecological framework. We used constant comparative method with double coders for theme emergence. Our results highlight a multitude of facilitators and barriers to engagement. Facilitators included: (1) individual—delivery preparedness and social support; (2) environmental—medical team relationships; and (3) societal—access to perinatal care. Barriers included: (1) individual—transfer stressors, medical needs, mental health, and dependents; (2) environmental—NICU space, communication, and lack of technology; and (3) societal—lack of paid leave. NICU parents with geographic separation from home experienced a multitude of barriers to engagement, many of which could be addressed by hospital-based interventions.
1. Introduction
More than 10% of U.S.-born infants are born prematurely and experience a birth hospitalization of weeks to months [1,2]. Families experience limitations on frequency and quantity of care they can provide to their infants during neonatal intensive care unit (NICU) admission. Individual and systemic barriers to engagement include the stress and trauma of preterm delivery, the physical environment of the NICU, socioeconomic stressors, limited English proficiency, and lack of paid leave [3,4,5]. These factors limit the ability to which families can engage in family-centered care (FCC), an approach to medical care based on the belief that optimal health outcomes are achieved when family members are active participants in providing social, emotional, and developmental support [6]. In the NICU, FCC supports and allows parents to participate more fully in caring for and making medical decisions for their infants.
Qualitative research has identified barriers to FCC including caregiving responsibilities and lack of family support [3,4]. The positive impacts of integrating parents is well established, as in, for example, through processes such as kangaroo care and family integrated care [7,8]. However, among families who are geographically displaced from home during their infant’s NICU admission, little is known specifically about the impact of distance on the factors that affect a parent’s ability to be physically present to provide care to their infant in the NICU [7,8,9].
Previous work has demonstrated an inverse association between both distance and travel time to the hospital with parental presence in the NICU [10]. Factors including postpartum medical issues, financial strain, and employment obligations may be more pronounced with geographic separation [11,12,13]. For families residing further away and in rural locations, preterm delivery and postnatal transfer are common and opportunities for back-transport closer to home are limited [14,15]. We hypothesized that families who are geographically displaced from home will disproportionally experience barriers and challenges that are different compared to the general NICU population.
Our study objective was to explore facilitators and barriers that families of very preterm infants (≤32 weeks gestational age, VPT) encounter with physical presence and engagement in the NICU, when geographically displaced from their primary residence.
2. Methods
2.1. Study Design
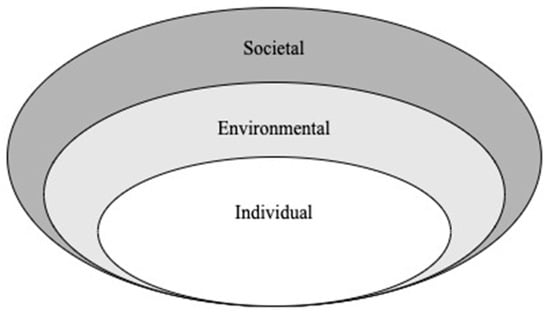
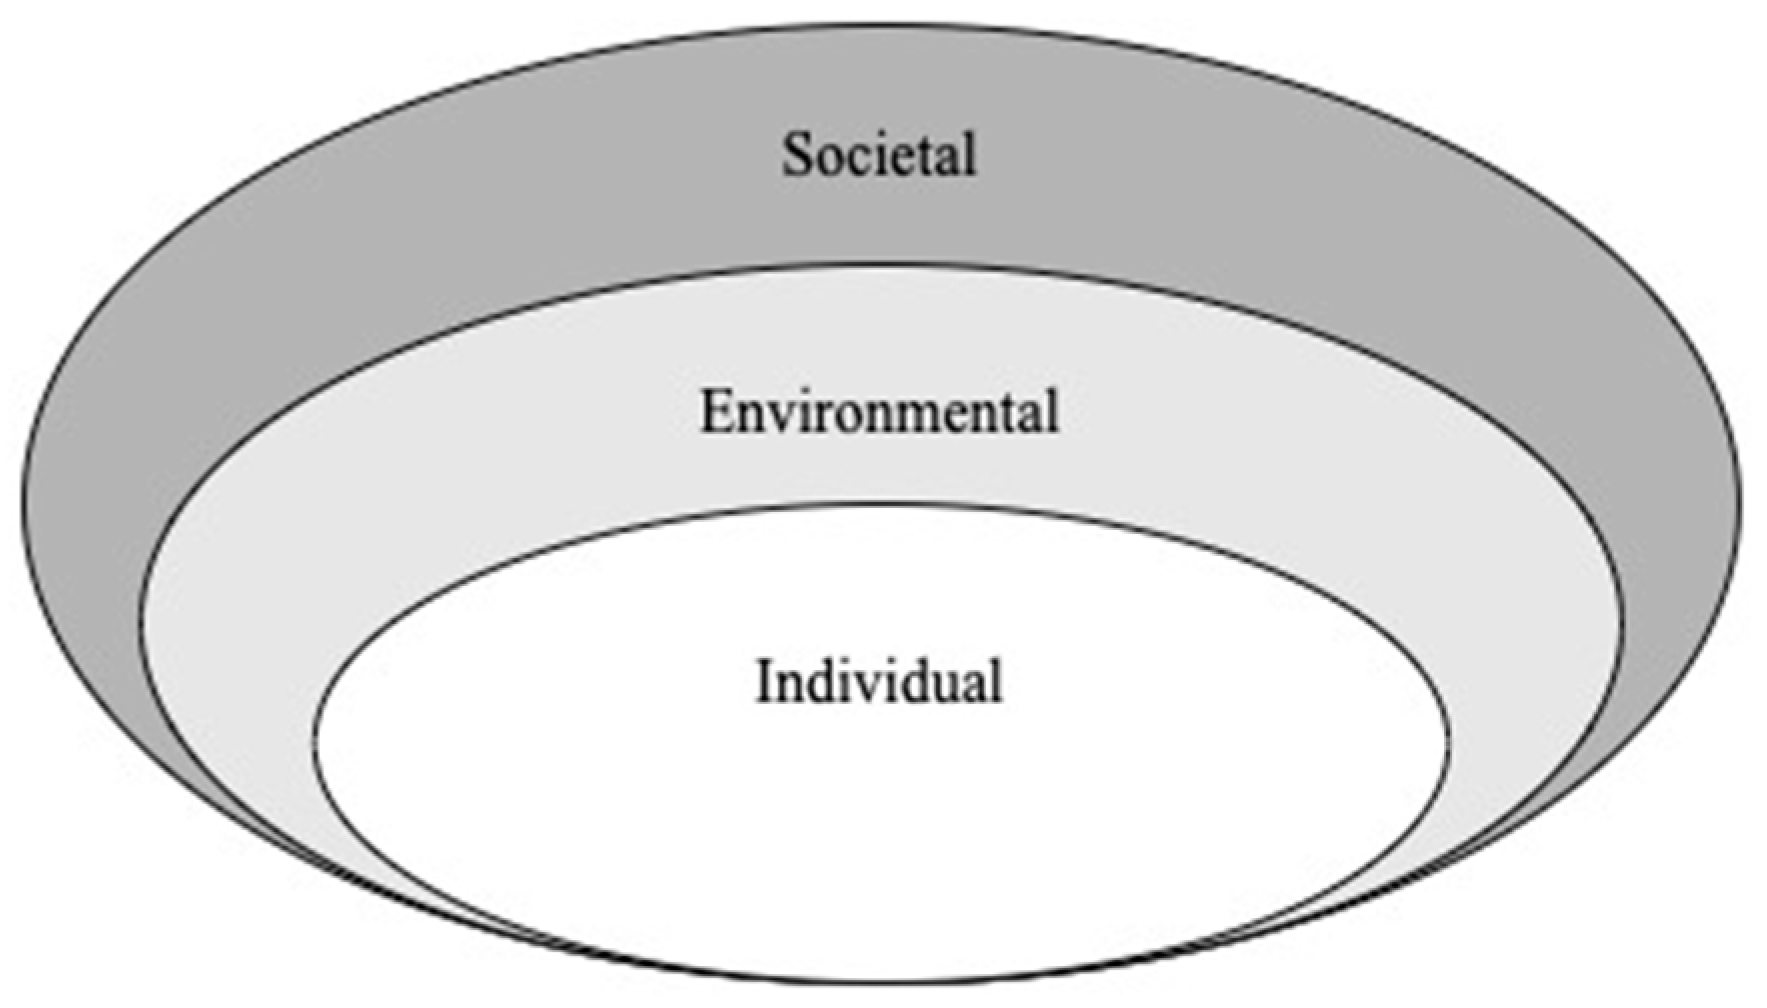
Using a socio-ecological conceptual framework, this qualitative study examined the impact of distance from home on the parental experience during a prolonged birth hospitalization [16]. We adapted grounded theory by using this framework, illustrated in Figure 1, to inform development of the interview guide and overall reporting of results. Rather than implementing theoretical sensitivity as typical in traditional grounded theory, we entered the research setting with predetermined ideas of parental engagement in the NICU setting. In this study, we explored: (a) individual-level factors associated directly with the parent, infant or parent-infant dyad; (b) environmental-level factors including the physical NICU space, interaction with medical providers and unit-level policies impacting parental engagement in the NICU; and (c) societal-level factors including the impact of state policies and availability of community support programs.
Figure 1.
Socio-ecological conceptual model.
2.2. Participants, Context, and Recruitment
Inclusion criteria included biologic or adoptive parents of VPT infants born at ≤32 weeks gestation and whose primary residence was ≥50 miles from the hospital. Participants were recruited from a regional level IV NICU, situated on an academic medical campus with a multi-state catchment area. Location of birth was defined as inborn, preterm infants born in the hospital with the level IV NICU or outborn, preterm infants born elsewhere and transferred postnatally. Urban or rural residence was defined by county at time of delivery. Urban counties are defined by the Office of Management and Budget (OMB) as those with an urban core of 50,000 or more people and rural counties are defined as those that are not urban.
Recruitment was conducted consecutively and families who had been admitted for at least 14 days were approached for consent via telephone. Fourteen days was chosen to provide sufficient NICU exposure and time beyond the acute admission experience for families. A total of 18 participants met eligibility criteria, of whom 72% consented to participate. Participants were compensated for participation with a USD 40 gift card and this study was approved by the Colorado Multiple Institutional Review Board.
2.3. Data Collection
A semi-structured interview guide used the socio-ecological model to evaluate the individual, environmental, and societal factors that impacted parents’ NICU experience [17,18]. The interview guide was piloted by parent research partners and edited to ensure it included relevant topics (Table 1). The interviews were conducted by a qualitatively trained Ph.D. research team member who did not provide medical care to the participants’ infant(s). In-depth interviews were conducted remotely by phone or video. Interviews were conducted until saturation was achieved, where no new information was shared by participants. Interviews were transcribed for analysis using an independent transcription service.
Table 1.
Abbreviated semi-structured interview guide.
2.4. Analysis
Transcripts were validated and inputted to NVivo 12 [19]. We used open, axial, and selective coding to allow themes to initially emerge, inform adjustments to the socio-ecological framework as it relates to this study, and develop a better understanding of facilitators and barriers for families of VPT infants to engage in the NICU when displaced from their primary residence [20]. Two coders (the interviewer and a neonatologist health services researcher) coded inductively to develop an iterative codebook. We participated in coding consistency meetings, utilizing the kappa statistic (with a benchmark greater than 0.6) to assess inter-rater reliability and to guide discussions to reach consensus on code definitions [21]. We double coded three transcripts (23%) to assess consistency and then distributed remaining transcripts for individual coding. The primary coder wrote a memo for each transcript to ensure retention of ideas and to synthesize concepts. The research team then generated memos for main themes across participants. Several steps were taken to ensure rigor in the analysis. The research team, including clinical and methodological experts, used an iterative approach to analysis to adjust interview questions including more targeted questions about the impact of distance, develop themes, and monitor for thematic saturation. We triangulated information in our data collection and conducted peer debriefing with NICU staff to elicit feedback on our findings and to allow for researchers to be reflexive in the research process, questioning our own potential biases and assumptions [22].
3. Results
3.1. Participant Characteristics
Demographics of the thirteen participants are outlined in Table 2. Overall, participants’ primary residence was an average of 285 miles from the hospital, ranging from 51 to 1643 miles distance. Most participants lived in state (77%), while 23% participants lived out of state.
Table 2.
Participant demographics and infant characteristics.
Below, we present facilitators followed by barriers to engagement at the individual, environmental, and societal levels with illustrative quotes outlined in Table 3 and Table 4. Individual facilitators related to preparedness for delivery and readiness for discharge; environmental facilitators included relationships with the medical team and use of technology, while societal factors were related to post-discharge services. Postnatal transfers, infant medical care, perinatal mental health, and readiness for discharge were individual-level barriers, while environmental barriers included the physical NICU environment, other dependents, the medical team’s inconsistency, and lack of access to technology; societal barriers were paid leave and unfamiliarity with post-discharge services.
Table 3.
Illustrative quotes: facilitators.
Table 4.
Illustrative quotes: barriers.
3.1.1. Theme 1: Individual Facilitators to Engagement
Preparedness for Delivery: Compared to parents of inborn infants, parents of outborn infants had an overall more heterogeneous prenatal experience including prenatal counseling and antepartum admission. For inborn infants, the antepartum period allowed for introduction to the NICU and enabled an increased sense of preparedness for delivery.
Social Support: Almost all participants discussed their social supports, especially among those who lived far away from the hospital. Participants highlighted how these individuals provided additional tangible support with food, financial resources, and childcare, and served as a primary source of emotional support. For those who lived far away, social supports available through the hospital, like the chaplain and other NICU parents, were particularly helpful.
Readiness for Discharge: Nearly all participants discussed how they were preparing for discharge from an emotional and technical standpoint. Many discussed how their time in the NICU had prepared them for home by better understanding the needs of their infant, how to care for them and what to anticipate post discharge. The impact of distance was especially notable for families who resided out of state or several hundred miles away and were less likely to receive consistent follow-up care at the regional children’s hospital.
3.1.2. Theme 2: Environmental Facilitators to Engagement
Medical Team/Ancillary Staff: Beyond individual facilitators to engagement, many participants discussed the guidance and support they had received from their medical team at the hospital. Some explained how hospital staff, in particular bedside nurses, had supported them in becoming comfortable with their infant’s care. This ranged from education from lactation to nurses understanding a parent’s comfort level with conducting infant cares, feeding, and skin-to-skin.
Technology: The use of technology for communication was mentioned by many participants and included the use of video chat and the power of social media to engage with additional community supports. A few participants who lived far away shared that they appreciated the ability to check the MyChart application while not at the bedside for updated medical information, as they were not always able to be physically present in the NICU.
3.1.3. Theme 3: Societal Facilitators to Engagement
Post-discharge Services: All participants shared about their infant’s medical needs when transitioning to care at home and anticipating the need for specialized equipment and services, such as therapists and pediatric subspecialists, regardless of geography. Out-of-state participants also shared perspectives regarding the importance of available therapy services to support their infant’s development.
In addition to facilitators, we heard about many barriers to parental physical presence and ability to engage in the NICU.
3.1.4. Theme 4: Individual Barriers to Engagement
Postnatal Transfer: Participants who delivered at an outside hospital and experienced subsequent transfer had more heterogenous experiences than those with inborn infants. Experience ranged from emergent and immediate postnatal transfer to a planned transfer for subspeciality consultation. One participant described the sudden postnatal transfer to be worrisome and difficult because they were uncertain if their child survived the journey.
Infant Medical Care: Participants who were unable to stay full-time at the hospital and lived further away from the hospital described emotional difficulty in feeling comfortable with their infant’s care while away from the bedside. This difficulty often stemmed from not being able to quickly be present with their infant.
Perinatal Mood and Anxiety Disorders (PMADs): Many participants discussed feelings of depression, anxiety, grief, guilt, and isolation while in the NICU. Several participants noted that it was mentally challenging to engage and bond with their infant, and thus were unable to realize their parental role and lacked control in caring for their infant.
Readiness for Discharge: While readiness for discharge was identified as a facilitator for engagement by some participants, others noted feeling nervous as they prepared for the transition home. These feelings related to not having their in-person nursing support team or the aid of cardiopulmonary monitors, especially if they lived further away from a clinic or hospital.
3.1.5. Theme 5: Environmental Barriers to Engagement
Physical NICU Environment: Many participants shared that while single patient rooms allowed for privacy, the physical setup was not conductive for a prolonged stay both in terms of comfort and noise level. An overall lack of understanding and information regarding the use of machines and wires attached to the infants was cited as a source of stress.
Presence of Other Dependents: For participants with other children, restrictions on sibling visitation during the COVID-19 pandemic impacted the time they were able to spend with their infant, resulting in shorter or infrequent visits. This was shared as a challenge both emotionally and with regards to being able to be physically present for all their children.
Medical Team: While the support of the medical team was described as a facilitator for engagement for some participants, others noted how the medical team could also present barriers for their engagement. Several participants commented on the frustration with having an inconsistent nursing and physician team caring for their infants, often resulting in a lack of continuity of care. For example, one participant commented that with an unfamiliar nurse, she had missed dressing her infant in clothes for the first time, an experience she had been anticipating for weeks.
Access to Technology: A commonly discussed suggestion among participants was optimizing the use of technology for times when parents are not able to be physically present in the NICU. Several participants would have appreciated the opportunity to visit their infant virtually through secure webcam or video.
3.1.6. Theme 6: Societal Barriers to Engagement
Employment and Paid Parental Leave: All participants shared about societal barriers to engagement and regardless of their geography, discussed their or their partner’s current employment situation. Among those who were working prior to delivery, most participants expressed accessing unpaid time off or applying for short-term disability for either themselves or their partners.
Post-Discharge Services: While all participants shared about their infant’s medical needs when transitioning to care at home, some identified post-discharge services as potential barriers to engagement. These included insurance challenges and availability of durable medical equipment and services such as outpatient therapy. One participant noted that hospital staff were not as familiar with out-of-state referrals and establishing necessary insurance coverage for these patients.
4. Discussion
This study aimed to explore facilitators and barriers that families of VPT infants in the NICU encounter with physical presence and engagement, when geographically displaced from their primary residence. We describe several facilitators and barriers to family engagement when displaced far from home during a prolonged birth hospitalization, which, for this population, appear to be magnified compared to the general NICU population. Within the socio-ecological framework, we found preparedness for delivery, social support, and readiness for discharge to be facilitators to engagement at the individual level. Environmental facilitators to engagement were related to relationships with the medical team/ancillary staff and use of technology. Societal facilitators were related to post-discharge services and access to outpatient subspeciality care. Conversely, individual barriers included fears and anxiety around postnatal transfer. Environmental barriers were related to challenges of the physical NICU environment, other dependents, and lack of access to technology. Societal barriers included employment, paid parental leave challenges, and availability and access to post-discharge services.
At the individual level, communicating expectations surrounding preterm delivery and potential transfer, while often challenging to predict, can help parents prepare for what is to come. Providing timely information with updates as clinical circumstances change and engaging in honest communication are qualities regarded as important for parents [23]. Social support for families experiencing geographic separation from home is paramount as many are disconnected from their usual social networks and are faced with unprecedented medical, family, and logistical challenges. Specifically, screening and addressing PMADs is crucial, especially for families who are displaced from home and less likely to access primary care or obstetric providers known to them. At baseline, PMAD prevalence in the preterm population exceeds that of the term population and is often under- and undiagnosed [24,25]. Hospital-based initiatives including universal screening during admission and integration of mental health professionals are opportunities to identify and provide resources to this high-risk population who may specifically benefit from telehealth or local referrals close to the NICU [26,27,28].
At the environmental level, the NICU layout plays a key role in parental ability to be physically present and engaged. Numerous studies have demonstrated the benefits of single-family rooms versus open-bay NICUs including increased breastfeeding rates and skin-to-skin time and decreased rates of sepsis [29,30]. While single-family rooms are associated with decreased parental stress, they may contribute to parental isolation and a decreased sense of community within the unit [31]. Maintaining the benefits of single-family rooms and encouraging peer support is one approach to supporting families, especially for those experiencing geographic separation from their home network. This concept was supported by parents in our study, many of whom used their infant’s NICU room as a home away from home if they were unable to frequently travel back to their primary residence.
As technology gains sophistication and accessibility, there is growing pressure to integrate this technology at the bedside [32]. The integration of live video for families to view their infant while not physically present in the NICU, is not currently available in our unit. The use of video visits has been associated with decreased parental stress during periods of infant separation and increased perceived parental involvement [33]. Furthermore, the use of video visits throughout NICU admission resulted in increased provision of breastmilk at discharge [34]. Using video conferencing technology to include parents not physically present in daily medical rounds may be one strategy to overcome geographic barriers for families and to include all caregivers in decision making. The use of technology to support families during admission to the NICU has been well studied internationally with use of secure video messaging systems and live video streaming [35,36,37].
From a societal perspective, achieving equitable paid leave for parents remains an urgent national priority. Benefits of paid leave include decreased odds of both infant and maternal readmission along with improved postpartum stress management [38]. Beyond paid leave, employment policies including flexible hours and remote working are opportunities to allow families of hospitalized infants to be physically present and engage with their infant while remaining in the workforce. This is particularity salient for families who live further away from the hospital, making commuting on a regular basis impracticable. We acknowledge that this impact differs based on local and national paid leave policies and impacts families differently depending on their residence. For example, families residing in countries with well-supported family leave policies may not experience these same barriers to engagement during NICU admission.
Attention to social determinants of health is imperative, especially for families who reside further away from the hospital and are more likely to experience higher expenses and challenges associated with spending time with their infant in the NICU [39]. Childcare, food and housing instability, transportation challenges and employment are infrequently assessed, leaving a gap for resource referral and follow-up. Inclusion of universal and comprehensive screening for SDoH during a prolonged NICU admission is critical to systematically identifying at-risk families [40].
5. Limitations
This study is limited by consecutive sampling and is not intended to reflect the experiences of all families of VPT infants. Results may vary for infants cared for in a different NICU setting with different access to resources, degree of family-centered care or social supports. As an exploratory study, it may contain inherent biases including sampling bias towards parents who felt strongly about sharing their experience. Despite these limitations, our study offers nuanced insight into the experiences of parental engagement, particularly for parents who are geographically displaced from their homes, grounded in lived experiences and supported by rigor in our conduct of double coding, data triangulation, and expert debriefs.
6. Conclusions
Participants identified several areas of improvement that have potential to specifically impact the experience for families who reside further away from the hospital. These include access to technology and improved communication around discharge. With the identification of these gaps, there is an opportunity for hospital-based interventions to improve parental engagement for this population.
Author Contributions
S.L.B. was responsible for designing the study, writing the protocol and iterative interview guide, coding the transcribed interviews, writing the manuscript. V.N.W. was responsible for conducting the interviews, coding the transcribed interviews, reviewing, and editing the. J.S. was responsible for screening potentially eligible participants, consenting participants, reviewing the manuscript. S.S.H. was responsible for overseeing the project protocol, providing mentorship, reviewing, editing the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This publication was supported by the PEDSnet Scholars Training Program, which is a national faculty development program that trains individuals in the competencies of learning health systems science.
Institutional Review Board Statement
This study was conducted in accordance with the Declaration of Helsinki, and approved by the Colorado Multiple Institutional Review Board of the University of Colorado (protocol code 19-2392, approved 1 March 2020).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
Transcript data from the qualitative interviews conducted for this study are protected due to subject privacy.
Conflicts of Interest
The authors declare no conflict of interest.
References
- March of Dimes 2021 March of Dimes Report Card. Available online: https://www.marchofdimes.org/2021-march-dimes-report-card (accessed on 12 February 2022).
- Lee, H.C.; Bennett, M.V.; Schulman, J.; Gould, J.B.; Profit, J. Estimating Length of Stay by Patient Type in the Neonatal Intensive Care Unit. Am. J. Perinatol. 2016, 33, 751–757. [Google Scholar] [PubMed]
- Klawetter, S.; Neu, M.; Roybal, K.L.; Greenfield, J.C.; Scott, J.; Hwang, S. Mothering in the NICU: A Qualitative Exploration of Maternal Engagement. Soc. Work Health Care 2019, 58, 746–763. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neu, M.; Klawetter, S.; Greenfield, J.C.; Roybal, K.; Scott, J.L.; Hwang, S.S. Mothers’ Experiences in the NICU Before Family-Centered Care and in NICUs Where It Is the Standard of Care. Adv. Neonatal Care 2020, 20, 68–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palau, M.A.; Meier, M.R.; Brinton, J.T.; Hwang, S.S.; Roosevelt, G.E.; Parker, T.A. The Impact of Parental Primary Language on Communication in the Neonatal Intensive Care Unit. J. Perinatol. 2019, 39, 307–313. [Google Scholar] [CrossRef] [Scilit]
- Eichner, J.M.; Johnson, B.H. Committee on Hospital Care and Institute for Patient- and Family-Centered Care Patient- and Family-Centered Care and the Pediatrician’s Role. Pediatrics 2012, 129, 394–404. [Google Scholar]
- O’Brien, K.; Robson, K.; Bracht, M.; Cruz, M.; Lui, K.; Alvaro, R.; da Silva, O.; Monterrosa, L.; Narvey, M.; Ng, E.; et al. Effectiveness of Family Integrated Care in Neonatal Intensive Care Units on Infant and Parent Outcomes: A Multicentre, Multinational, Cluster-Randomised Controlled Trial. Lancet Child Adolesc. Health 2018, 2, 245–254. [Google Scholar] [CrossRef] [Scilit]
- Charpak, N.; Tessier, R.; Ruiz, J.G.; Hernandez, J.T.; Uriza, F.; Villegas, J.; Nadeau, L.; Mercier, C.; Maheu, F.; Marin, J.; et al. Twenty-Year Follow-up of Kangaroo Mother Care Versus Traditional Care. Pediatrics 2017, 139, e20162063. [Google Scholar] [CrossRef] [Scilit]
- Campbell-Yeo, M.L.; Disher, T.C.; Benoit, B.L.; Johnston, C.C. Understanding Kangaroo Care and Its Benefits to Preterm Infants. Pediatr. Health Med. Ther. 2015, 6, 15–32. [Google Scholar] [CrossRef] [Scilit]
- Bourque, S.L.; Weikel, B.W.; Palau, M.A.; Greenfield, J.C.; Hall, A.; Klawetter, S.; Neu, M.; Scott, J.; Shah, P.; Roybal, K.L.; et al. The Association of Social Factors and Time Spent in the NICU for Mothers of Very Preterm Infants. Hosp. Pediatr. 2021, 11, 988–996. [Google Scholar] [CrossRef] [Scilit]
- Noergaard, B.; Ammentorp, J.; Garne, E.; Fenger-Gron, J.; Kofoed, P.-E. Fathers’ Stress in a Neonatal Intensive Care Unit. Adv. Neonatal Care 2018, 18, 413–422. [Google Scholar] [CrossRef] [Scilit]
- Lorch, S.A. Perinatal Legislative Policies and Health Outcomes. Semin. Perinatol. 2017, 41, 375–384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Verbiest, S.; Ferrari, R.; Tucker, C.; McClain, E.K.; Charles, N.; Stuebe, A.M. Health Needs of Mothers of Infants in a Neonatal Intensive Care Unit: A Mixed-Methods Study. Ann. Intern. Med. 2020, 173, S37–S44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bourque, S.L.; Weikel, B.W.; Crispe, K.; Hwang, S.S. Association of Rural and Frontier Residence with Very Preterm and Very Low Birth Weight Delivery in Nonlevel III NICUs. Am. J. Perinatol. 2021, 40, 35–41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bourque, S.L.; Levek, C.; Melara, D.L.; Grover, T.R.; Hwang, S.S. Prevalence and Predictors of Back-Transport Closer to Maternal Residence After Acute Neonatal Care in a Regional NICU. Matern. Child Health J. 2019, 23, 212–219. [Google Scholar] [CrossRef] [Scilit]
- Tolley, E.E.; Ulin, P.R.; Mack, N.; Robinson, E.T.; Succop, S.M. Qualitative Methods in Public Health: A Field Guide for Applied Research, 2nd ed.; John Wiley & Sons: Hoboken, NJ, USA, 2016; Volume 2. [Google Scholar]
- Kallio, H.; Pietilä, A.-M.; Johnson, M.; Kangasniemi, M. Systematic Methodological Review: Developing a Framework for a Qualitative Semi-Structured Interview Guide. J. Adv. Nurs. 2016, 72, 2954–2965. [Google Scholar] [CrossRef] [Scilit]
- Peters, K.; Halcomb, E. Interviews in Qualitative Research. Nurse Res. 2015, 22, 6–7. [Google Scholar] [CrossRef] [Scilit]
- Houghton, C.; Murphy, K.; Meehan, B.; Thomas, J.; Brooker, D.; Casey, D. From Screening to Synthesis: Using Nvivo to Enhance Transparency in Qualitative Evidence Synthesis. J. Clin. Nurs. 2017, 26, 873–881. [Google Scholar] [CrossRef] [Scilit]
- Charmaz, K. Constructing Grounded Theory, 2nd ed.; Sage Publications, Ltd.: Southend Oaks, CA, USA, 2014. [Google Scholar]
- McHugh, M.L. Interrater Reliability: The Kappa Statistic. Biochem. Med. 2012, 22, 276–282. [Google Scholar] [CrossRef] [Scilit]
- Engward, H.; Davis, G. Being Reflexive in Qualitative Grounded Theory: Discussion and Application of a Model of Reflexivity. J. Adv. Nurs. 2015, 71, 1530–1538. [Google Scholar] [CrossRef] [Scilit]
- Kharrat, A.; Moore, G.P.; Beckett, S.; Nicholls, S.G.; Sampson, M.; Daboval, T. Antenatal Consultations at Extreme Prematurity: A Systematic Review of Parent Communication Needs. J. Pediatr. 2018, 196, 109–115.e7. [Google Scholar] [CrossRef] [Scilit]
- Johnson Rolfes, J.; Paulsen, M. Protecting the Infant-Parent Relationship: Special Emphasis on Perinatal Mood and Anxiety Disorder Screening and Treatment in Neonatal Intensive Care Unit Parents. J. Perinatol. 2021, 42, 815–818. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cox, E.Q.; Sowa, N.A.; Meltzer-Brody, S.E.; Gaynes, B.N. The Perinatal Depression Treatment Cascade: Baby Steps toward Improving Outcomes. J. Clin. Psychiatry 2016, 77, 1189–1200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saxton, S.N.; Dempsey, A.G.; Willis, T.; Baughcum, A.E.; Chavis, L.; Hoffman, C.; Fulco, C.J.; Milford, C.A.; Steinberg, Z. Essential Knowledge and Competencies for Psychologists Working in Neonatal Intensive Care Units. J. Clin. Psychol. Med. Settings 2020, 27, 830–841. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scheans, P.; Mischel, R.; Munson, M.; Bulaevskaya, K. Postpartum Mood Disorders Screening in the NICU. Neonatal Netw. 2016, 35, 240–242. [Google Scholar] [CrossRef] [Scilit]
- Murthy, S.; Haeusslein, L.; Bent, S.; Fitelson, E.; Franck, L.S.; Mangurian, C. Feasibility of Universal Screening for Postpartum Mood and Anxiety Disorders among Caregivers of Infants Hospitalized in NICUs: A Systematic Review. J. Perinatol. 2021, 41, 1811–1824. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Domanico, R.; Davis, D.K.; Coleman, F.; Davis, B.O. Documenting the NICU Design Dilemma: Comparative Patient Progress in Open-Ward and Single Family Room Units. J. Perinatol. 2011, 31, 281–288. [Google Scholar] [CrossRef] [Scilit]
- Lester, B.M.; Hawes, K.; Abar, B.; Sullivan, M.; Miller, R.; Bigsby, R.; Laptook, A.; Salisbury, A.; Taub, M.; Lagasse, L.L.; et al. Single-Family Room Care and Neurobehavioral and Medical Outcomes in Preterm Infants. Pediatrics 2014, 134, 754–760. [Google Scholar] [CrossRef] [Scilit]
- Liu, L.X.; Mozafarinia, M.; Axelin, A.; Feeley, N. Parents’ Experiences of Support in NICU Single-Family Rooms. Neonatal Netw. 2019, 38, 88–97. [Google Scholar] [CrossRef] [Scilit]
- Richardson, B.; Dol, J.; Rutledge, K.; Monaghan, J.; Orovec, A.; Howie, K.; Boates, T.; Smit, M.; Campbell-Yeo, M. Evaluation of Mobile Apps Targeted to Parents of Infants in the Neonatal Intensive Care Unit: Systematic App Review. JMIR Mhealth Uhealth 2019, 7, e11620. [Google Scholar] [CrossRef] [Scilit]
- Guttmann, K.; Patterson, C.; Haines, T.; Hoffman, C.; Masten, M.; Lorch, S.; Chuo, J. Parent Stress in Relation to Use of Bedside Telehealth, an Initiative to Improve Family-Centeredness of Care in the Neonatal Intensive Care Unit. J. Patient Exp. 2020, 7, 1378–1383. [Google Scholar] [CrossRef] [Scilit]
- Weber, J.C.; Sohn, K.; Sauers-Ford, H.S.; Hanhauser, A.; Tancredi, D.J.; Marcin, J.P.; Hoffman, K.R. Impact of a Parent Video Viewing Program in the Neonatal Intensive Care Unit. Telemed. e-Health 2021, 27, 679–685. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kirolos, S.; Sutcliffe, L.; Giatsi Clausen, M.; Abernethy, C.; Shanmugalingam, S.; Bauwens, N.; Orme, J.; Thomson, K.; Grattan, R.; Patel, N. Asynchronous Video Messaging Promotes Family Involvement and Mitigates Separation in Neonatal Care. Arch. Dis. Child. Fetal Neonatal Ed. 2021, 106, 172–177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bott, S.; Dantas Fernandez, N.; Narciso, J.; MacAlpine, J.; Quain, N.; Rettie, J.; Sharpe, L.; Diambomba, Y.; Al Bizri, A.; O’Brien, K.; et al. Building Connections with Families: Implementation of a Video-Messaging Service in the Neonatal Intensive Care Unit. Children 2023, 10, 1338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gallagher, K.; Hayns-Worthington, R.; Marlow, N.; Meek, J.; Chant, K. Parental Experiences of Live Video Streaming Technology in Neonatal Care in England: A Qualitative Study. BMC Pediatr. 2023, 23, 107. [Google Scholar] [CrossRef] [Scilit]
- Jou, J.; Kozhimannil, K.B.; Abraham, J.M.; Blewett, L.A.; McGovern, P.M. Paid Maternity Leave in the United States: Associations with Maternal and Infant Health. Matern. Child Health J. 2018, 22, 216–225. [Google Scholar] [CrossRef] [Scilit]
- Johnson, D.; Howard, E.D. Screening for the Social Determinants of Health: An Ethical Imperative. J. Perinat. Neonatal Nurs. 2020, 34, 289. [Google Scholar] [CrossRef] [Scilit]
- Parker, M.G.; Garg, A.; Brochier, A.; Rhein, L.M.; Forbes, E.S.; Klawetter, S.; Drainoni, M.-L. Approaches to Addressing Social Determinants of Health in the NICU: A Mixed Methods Study. J. Perinatol. 2021, 41, 1983–1991. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).