


Abstract
Implantable cardioverter-defibrillators (ICDs) were historically viewed as a barrier to vigorous or competitive sport participation, based on theoretical concerns about arrhythmia induction, inappropriate shocks, device damage, and shock-related injury during activity. Contemporary registry data have reframed this paradigm, demonstrating that selected athletes with ICDs can participate in organized sport without the catastrophic outcomes once feared, although these data remain reassuring rather than definitive given selection bias and underrepresentation of high-consequence sports. This review synthesizes contemporary athlete-specific registry data and broader randomized device and programming evidence, alongside current guideline recommendations, to provide a practical framework for the care of athletes with ICDs, addressing indications, which should remain diagnosis-driven rather than sport-driven; device selection, weighing transvenous, subcutaneous, and extravascular platforms against an athlete’s pacing needs, anatomy, and sport-specific trauma risk; and exercise-informed device programming. We then present a longitudinal framework integrating clinical readiness, device readiness, sport-specific risk, emergency preparedness, shared decision-making, and reassessment after clinical or sporting changes. Special populations and priorities for future research are also discussed. Rather than a binary clearance decision, modern management of athletes with ICDs requires an individualized, longitudinally reassessed approach to risk.
1. Introduction
For decades, the presence of an implantable cardioverter-defibrillator (ICD) in an athlete was viewed as a barrier to vigorous or competitive sport participation. This cautious stance reflected concerns that intense exercise might increase the risk of ventricular arrhythmias, provoke inappropriate ICD shocks due to sinus tachycardia or supraventricular arrhythmias, damage the device or its leads, place the athlete at serious risk if syncope or a shock occurred during activity, or impair the ability of an ICD shock to terminate an arrhythmia. Consequently, earlier eligibility guidelines generally recommended restriction, particularly from competitive, high-intensity, collision, or other high-consequence sports [1,2,3,4].
Contemporary evidence has shifted this paradigm. Prospective registry data and longer-term follow-up studies have demonstrated that selected athletes with ICDs can participate in vigorous and competitive sports without the catastrophic outcomes that had previously been feared [5,6,7,8,9]. Reflecting these data, the 2025 AHA/ACC Clinical Considerations for Competitive Sports Participation for Athletes With Cardiovascular Abnormalities scientific statement considers competitive sports participation reasonable for athletes with an ICD after individualized risk assessment and shared decision-making. Participation in collision or impact sports can also be considered, provided that the discussion specifically addresses the potential for ICD-system damage or malfunction [10]. Importantly, an ICD mitigates the risk of malignant ventricular arrhythmia but does not eliminate the risk conferred by the underlying cardiac disease itself. Conditions such as arrhythmogenic cardiomyopathy, catecholaminergic polymorphic ventricular tachycardia, long QT syndrome, hypertrophic cardiomyopathy, and myocarditis each carry disease-specific considerations that persist independent of device protection and that inform return-to-sport decisions throughout this review.
These findings do not imply that sport participation is risk-free or appropriate for every ICD recipient. Rather, the clinical question has shifted from whether sport should be categorically prohibited to how clinicians can assess and mitigate risk through individualized counseling, device management, and return-to-sport planning.
In this review, we present a practical approach to caring for athletes with ICDs. We summarize the evidence that moved the field from broad restriction toward individualized return-to-sport decisions and integrate device selection, programming, sport-specific risk, emergency preparedness, and longitudinal reassessment. Our goal is to help clinicians support selected athletes in participating as safely as possible while acknowledging the uncertainties that should continue to inform counseling and follow-up.
Although the 2024 HRS consensus statement and the 2025 AHA/ACC scientific statement have substantially advanced guidance on ICD-specific return-to-sport decisions, both remain organized around broad, multi-condition eligibility recommendations rather than the device-level and workflow-level decisions clinicians face once an ICD is already indicated [9,10]. This review does not seek to supersede or duplicate these statements; rather, it translates their recommendations, together with device-selection and programming evidence not centrally addressed by either document, into an integrated, ICD-specific clinical workflow, and incorporates athlete-specific evidence published after these statements, including a 2025 meta-analysis of return-to-play outcomes [11], real-world subcutaneous ICD physical-activity data from the iSUSI registry [12], and recent case reports of exercise-guided subcutaneous ICD programming and extravascular ICD implantation in competitive athletes [13,14].
The 2024 HRS consensus statement and 2025 AHA/ACC scientific statement in the United States, and the 2020 ESC Sports Cardiology guidelines together with the 2022 ESC ventricular arrhythmia guideline in Europe, have converged on a broadly similar philosophy: shared decision-making has replaced categorical restriction as the governing principle for athletes with ICDs [4,9,10,15]. Some differences in emphasis remain. US documents typically stratify participation as competitive versus recreational, whereas the ESC guidelines add an explicit leisure-time category and, in ICD-specific decisions, direct clinicians to weigh explicitly that intensive sport increases the frequency of both appropriate and inappropriate shocks and the potential risk to third parties, considerations present but less explicitly operationalized in the US statements. Both frameworks also caution that they describe medical risk assessment rather than formal competition eligibility: in the United States, eligibility for interscholastic, collegiate, and professional competition is frequently determined separately by team, school, or league medical staff and governing bodies, while in Europe formal eligibility may be governed by national sports federations and international governing bodies, each of which may apply criteria that differ from, and in some cases are more restrictive than, the guideline recommendations reviewed here. Clinicians should treat this review, and the underlying HRS, AHA/ACC, and ESC documents, as decision support for medical risk assessment rather than a substitute for confirming an individual athlete’s formal eligibility with the relevant sporting authority.
Because sport-related terminology is used inconsistently across the literature, this review distinguishes recreational sport (undertaken primarily for personal enjoyment or fitness, without formal competition), competitive sport (organized participation with formal competition at any level), elite or professional sport (competition at the highest organized level, often with financial, contractual, or eligibility stakes), collision or contact sport (participation with expected or frequent direct bodily impact), and high-consequence sport (activities in which transient incapacitation carries a risk of death or catastrophic injury independent of the underlying arrhythmia, such as open-water swimming, scuba diving, climbing, or motorsport). These categories are not mutually exclusive, and an individual athlete’s risk is better characterized by the specific combination of physiologic demand, environment, and consequence of impairment than by any single label.
2. Evidence That Shifted the Field
Historically, sports eligibility recommendations for athletes with ICDs were conservative, largely because prospective data were limited and the consequences of device therapy or arrhythmic syncope during sport were uncertain [1,2,3,4]. The ICD Sports Safety Registry was therefore pivotal because it prospectively evaluated the outcomes that had driven these restrictions: death during sport, externally resuscitated tachyarrhythmia, shock-related injury, and failure of the device to terminate malignant ventricular arrhythmias [5]. Key studies informing contemporary sports participation recommendations for athletes with ICDs are summarized in Table 1.
Table 1.
Key evidence informing sports participation in athletes with implantable cardioverter-defibrillators.
In the original prospective, multinational registry, 372 athletes with ICDs, aged 10 to 60 years, were enrolled while participating in organized sports or activities considered high risk if a transient loss of control occurred [5]. Over a median follow-up of 31 months, there were no deaths, no resuscitated arrests, and no arrhythmia- or shock-related injuries during sports participation. ICD therapies were not rare: shocks occurred during competition or practice in 37 athletes (10% of the study population), during other physical activity in 29 athletes (8%), and at rest in 24 athletes (6%). Multiple shocks occurred during ventricular tachyarrhythmias, but the ICD ultimately terminated all episodes. Thus, the central message of the registry was not that vigorous sport eliminates arrhythmic risk, but that selected athletes could participate without the catastrophic outcomes that had historically driven broad restriction.
Longer-term and pediatric data reinforced this balanced message. In the extended follow-up of the ICD Sports Safety Registry, 440 athletes were followed for a median of 44 months, totaling 1446 person-years, again without sports-related death, externally resuscitated tachyarrhythmia, or serious arrhythmia- or shock-related injury [6]. In a subanalysis of 129 athletes aged 10 to 21 years, 35 athletes (27%) received 38 shocks, and one ventricular tachycardia (VT)/ventricular fibrillation (VF) storm occurred during competition, yet there were no deaths, arrests, or arrhythmia-related injuries during sports participation [7]. Lead malfunction-free survival was 92.3% at 5 years and 79.6% at 10 years, underscoring that long-term device durability remains important in young active patients [7]. The European cohort of intensive recreational athletes further broadened the relevance of these findings, emphasizing that counseling should be guided by physiologic demand and sport environment rather than by the label of “competitive” or “recreational” alone [8].
These data should be interpreted as reassuring but not definitive. Participants had a long time from implant to enrollment, many had already chosen to remain active despite their ICD, and many self-enrolled outside traditional recruitment pathways. This self-selection introduces a form of healthy-participant or survivor bias: athletes who continued competing after ICD implantation, and who agreed to enroll, are systematically different from those who stopped, were never referred, or declined participation. The underlying diseases and sports represented are also heterogeneous, and the number of athletes within any individual disease substrate is often small, limiting the precision of substrate-specific risk estimates. Collision sports, high-consequence sports, remote endurance activities, athletes with unstable arrhythmia profiles, and those with progressive cardiomyopathic substrates remain underrepresented or require cautious interpretation [5,6,7,8]. Taken together, this evidence base should be interpreted as reassuring for appropriately selected athletes rather than as demonstrating that unrestricted competitive sports participation is universally safe. In addition, much of the original prospective athlete data involved transvenous ICD (TV-ICD) systems and earlier programming strategies. A 2025 meta-analysis pooling these and related cohorts (six studies, 1183 athletes with TV-ICDs or S-ICDs) reported appropriate shock rates of 13% and inappropriate shock rates of 4%, with no shock-related physical injuries and a sports-discontinuation rate of only 2%, reinforcing the individual registries at the aggregate level while still relying on the same underlying observational, self-selected cohorts [11].
Newer device platforms further highlight the need for contemporary data. Subcutaneous ICDs (S-ICDs) may be attractive for young, active patients. Real-world data from the iSUSI registry suggest that S-ICDs can be used in athletes without an observed increase in overall device-related complications or inappropriate shocks compared with nonathletes, although myopotential oversensing and early post-implantation infections require attention [12]. Similarly, the multicenter S-ICD Rhythm Detect registry, which specifically stratified patients by self-reported physical activity level using a validated questionnaire, found no significant difference in arrhythmia- or device-related complications between inactive, moderately active, and highly active S-ICD recipients, further supporting the safety of an active lifestyle in appropriately selected S-ICD patients [17]. The ongoing SPORT S-ICD study was designed to prospectively evaluate sports participation among patients with S-ICDs [18]. Extravascular ICD (EV-ICD) systems and selected nontraditional approaches may expand options for athletes in whom avoiding intravascular leads is desirable, but athlete-specific outcome data remain limited [9,19].
3. Indications for ICD Implantation in Athletes
The decision to implant an ICD in an athlete should be driven by SCD risk rather than by the athlete’s desire to continue sport. Athletic participation may influence risk interpretation, counseling, device selection, programming, and follow-up, but it should not independently create an ICD indication. This distinction is particularly important in young athletes, for whom ICD implantation carries decades of potential shocks, generator changes, lead or system complications, body image concerns, eligibility implications, and psychological burden. Contemporary hypertrophic cardiomyopathy (HCM) guidance explicitly states that ICD placement solely to permit competitive athletics should not be performed [20].
ICD indications in athletes can be organized into three practical categories: secondary prevention, primary prevention, and gray areas. Secondary prevention indications are generally the most straightforward and include resuscitated SCA, sustained VT, VF, or hemodynamically significant ventricular arrhythmias not explained by a completely reversible cause [15]. Primary prevention decisions should be anchored in the underlying diagnosis and the quality of available risk markers. They are more nuanced and require substrate-specific risk assessment.
Gray areas arise when risk markers are incomplete, the phenotype is evolving, the event may have been partially reversible, or the athlete’s anticipated exercise exposure creates concern beyond what is captured by standard risk models. These most challenging scenarios are usually not clear indications. In these situations, clinicians should avoid using ICD implantation as a shortcut to permit sport participation or resolve uncertainty. Instead, the goal is to clarify the substrate, define the uncertainty, discuss the long-term consequences of device therapy, and separate the decision for sudden death prevention from the later decision about return to sport [9,15,20].
Maintaining this separation between diagnosis and desire preserves the integrity of sudden death prevention while allowing return-to-sport planning to focus on the factors most likely to reduce harm: substrate control, device selection, exercise-informed programming, emergency planning, and longitudinal reassessment.
4. Device Selection and Implantation Strategy in the Athlete
The optimal system depends on the athlete’s arrhythmic substrate, need for bradycardia pacing, ATP, cardiac resynchronization therapy (CRT), vascular access, anatomy, age, anticipated device longevity, sport type, and risk of trauma or repetitive mechanical stress. In athletes, the goal is not simply to implant a device capable of terminating VT or VF, but to select a system that provides durable protection while minimizing avoidable shocks, lead complications, pocket-related morbidity, and sport-specific limitations over years or decades of activity. A practical device-selection framework is summarized in Table 2.
Table 2.
Device selection and implantation considerations for athletes with implantable cardioverter-defibrillators.
The approach should begin by identifying clinical needs. Athletes who require chronic bradycardia pacing or cardiac resynchronization therapy require a transvenous system, since neither the S-ICD nor the EV-ICD provides these functions. Athletes who require ATP for monomorphic VT can be served by a transvenous ICD or, in selected cases, by an EV-ICD, which provides ATP and post-shock pacing but not chronic bradycardia support. In contrast, athletes without pacing needs who are young, have long-anticipated device exposure, or have a strong rationale for avoiding intravascular leads may be better suited for an S-ICD or EV-ICD. Recent case reports illustrate this individualized decision-making in practice, including exercise-guided S-ICD programming in a competitive athlete and EV-ICD implantation in a professional powerlifter, both without adverse effects on training or device function [13,14].
This decision process can be organized as a simple algorithm. The first branch point is pacing requirement: athletes with chronic bradycardia pacing or CRT indications require a transvenous system, since neither the S-ICD nor the EV-ICD provides these functions. Among athletes without a chronic pacing requirement, the second branch point is anticipated benefit from ATP: those with recurrent monomorphic VT likely to respond to ATP are candidates for a transvenous ICD or, in selected cases, an EV-ICD, while those without an ATP indication and with a strong rationale for avoiding intravascular leads are reasonable candidates for an S-ICD. Within each branch, the specific choice among transvenous, subcutaneous, and extravascular platforms is then refined by anatomy and vascular access, anticipated duration of device therapy, suitability of the athlete’s surface ECG for reliable sensing, sport-specific trauma exposure, and the athlete’s own preference after shared decision-making. Device-specific considerations are summarized in Table 3.
Table 3.
Quantitative comparison of transvenous, subcutaneous, and extravascular ICD platforms.
TV-ICDs remain the most versatile platform. The significant tradeoff is the long-term vulnerability of the transvenous lead. Young and active patients face cumulative exposure to lead fracture, insulation failure, venous obstruction, tricuspid valve interaction, infection, and extraction risk. In athletes participating in contact, collision, heavy resistance, or upper-body dominant sports, these risks should be discussed explicitly during device counseling and implantation planning [16].
S-ICDs are attractive for many athletes because they avoid the intravascular space and may reduce transvenous lead-related complications. In patients without pacing indications, randomized and prospective data support the safety and efficacy of S-ICD therapy [21,22,23]. However, the absence of bradycardia pacing, ATP, and CRT remains clinically important. S-ICDs may be less suitable for athletes with recurrent monomorphic VT, conduction disease, anticipated pacing needs, or substrates in which ATP could meaningfully reduce shocks.
S-ICD use in athletes also requires careful attention to sensing. Exercise may alter QRS amplitude, T-wave morphology, myopotential noise, respiratory pattern, and body position, all of which can affect sensing behavior. In athletic patients, S-ICD screening should ideally extend beyond resting vectors and include exercise testing, postural changes, and, when relevant, maneuvers that reproduce sport-specific myopotential noise or body position. This is especially important in athletes with high peak heart rates, potential T-wave changes during exertion, repetitive upper-extremity activity, prone positioning, trunk rotation, or direct chest wall contact.
Standard supine and upright screening at rest is an established, guideline-supported component of S-ICD candidacy assessment. Extending screening to exercise, posture changes, and sport-specific maneuvers is a reasonable, physiologically motivated extension of this practice, but it is supported predominantly by expert opinion and limited observational experience rather than by dedicated prospective trials and should be interpreted accordingly.
EV-ICD systems may offer an intermediate approach by avoiding intravascular leads while preserving selected pacing capabilities, including ATP and pause-prevention pacing. This concept is appealing for some athletes in whom transvenous lead avoidance is desirable but ATP or limited pacing support may still be clinically valuable [19,24]. However, these systems are newer than conventional TV-ICD and S-ICD platforms, and athlete-specific data remain limited. Their use should therefore be individualized.
Selected athletes may require nontraditional systems, including epicardial or hybrid approaches. These strategies are most relevant in complex congenital heart disease, limited venous access, intracardiac shunts, prior device infection, small body size, or anatomy that makes standard systems unfavorable. This may include an abdominal generator with epicardial pacing leads and pericardial or subcutaneous ICD coils, which could provide better protection from device harm.
Implantation strategy should account for the athlete’s sport before the procedure whenever possible. Pocket location, lead course, anchoring, equipment contact points, repetitive arm motion, and anticipated direct impact should be considered during preprocedural planning. For example, athletes in collision sports may be exposed to direct generator trauma; swimmers, rowers, climbers, baseball players, volleyball players, and weightlifters may place repetitive stress across the shoulder girdle; and cyclists, skiers, and runners may have sport-specific equipment or body positions that affect generator comfort. A lateral S-ICD generator may be well-tolerated in many patients but may be problematic in athletes exposed to direct thoracic impact, tight equipment, repetitive arm swinging, or prone positioning. Similarly, transvenous lead stress may be relevant in athletes with repetitive shoulder abduction, external rotation, heavy resistance training, falls, or collision exposure. These factors rarely determine device choice alone, but they should shape counseling, implantation approach, and follow-up.
The best device for an athlete is therefore not necessarily the newest or least invasive system, but the system that best matches the athlete’s arrhythmic risk, anatomy, sport exposure, and long-term management needs.
5. Device Programming in Athletes
Device programming is one of the most modifiable components of return-to-sport risk mitigation in athletes with ICDs. Athletes are vulnerable to inappropriate or avoidable therapies because exercise produces sustained sinus tachycardia, adrenergic surges, supraventricular arrhythmias, dynamic QRS and T-wave changes, myopotential noise, and body-position effects that may not be evident at rest. These factors can cause overlap between expected training heart rates and conventional detection zones, particularly in young athletes and those participating in high-intensity endurance sports. Therefore, ICD programming in athletes should be individualized rather than left at nominal or default settings.
The goal of programming is to reduce unnecessary therapies without compromising treatment of life-threatening VT. In broader ICD populations, high-rate detection thresholds, longer detection intervals, and modern discrimination algorithms reduce inappropriate or unnecessary therapies [25,26,27,28]. Athlete-specific data from the ICD Sports Registry support this approach directly: programming with higher rate cutoffs and longer detection intervals was associated with fewer inappropriate shocks and transient loss of consciousness without an increase in mortality [29]. These principles are highly relevant in athletes, but they must be applied in the context of the athlete’s substrate, prior arrhythmia history, and expected exercise physiology. An athlete with prior rapid VF may require a different programming strategy than an athlete with slower monomorphic VT that is consistently responsive to ATP. Similarly, athletes with frequent supraventricular tachycardia, atrial fibrillation, or sinus rates approaching standard therapy zones require careful discriminator programming and, when appropriate, treatment of the supraventricular arrhythmia substrate before return to sport. In practice, athlete-specific programming should aim to minimize inappropriate therapy from sinus tachycardia or supraventricular arrhythmias, reduce unnecessary therapy for nonsustained ventricular arrhythmias, preserve prompt treatment of malignant ventricular arrhythmias, confirm sensing during exertion, and prompt reassessment after a shock or meaningful clinical change.
Exercise testing is central to athlete-specific ICD programming. Maximal or sport-specific testing can define peak sinus rate, evaluate exertional ectopy, identify supraventricular arrhythmias, assess QRS and T-wave behavior, and reveal sensing abnormalities that are absent at rest [9]. When feasible, testing should approximate the athlete’s training conditions and then be used to determine appropriate detection zones and time to therapy.
In practice, this individualization can be organized as a sequential workflow. First, establish the athlete’s maximal or near-maximal physiologic sinus rate and typical training heart rate range through exercise or sport-specific testing. Second, document the rate and morphology of any previously recorded ventricular tachyarrhythmia, since therapy zones should be set with reference to the athlete’s own documented VT/VF rates rather than nominal defaults. Third, program detection and therapy zones with an adequate safety margin between the athlete’s peak sinus rate and the lowest programmed detection rate, using rhythm discrimination algorithms to further reduce inappropriate classification of supraventricular rhythms. Fourth, confirm adequate sensing during exercise testing, since myopotential noise, T-wave oversensing, and posture-dependent signal changes may only become apparent under exertional conditions. Fifth, interrogate the device after exercise testing and after any subsequent shock or clinical change to confirm that programming remains appropriate. This sequence does not require universal numerical thresholds, which are neither available nor appropriate given the heterogeneity of athletes and devices, but it does require that each step be performed deliberately rather than assumed.
Programming should be reassessed whenever the athlete’s clinical or training status changes. New symptoms, syncope, palpitations, appropriate or inappropriate ICD therapy, medication changes, catheter ablation, cardiomyopathy progression, or meaningful changes in training intensity should prompt device review. Remote monitoring can support early recognition of arrhythmia episodes, lead or sensing abnormalities, and therapy delivery, but it should not replace structured follow-up during return to high-intensity sport. Its ability to detect events earlier should not be equated with evidence that remote monitoring itself reduces sports-related adverse outcomes, which has not been directly demonstrated in athletes.
Programming deserves the same deliberate attention as device selection, not a settings checklist to finish and forget. The safest approach is iterative: define the athlete’s peak physiologic sinus rate, understand the arrhythmic substrate, program detection and therapy zones with appropriate safety margins, test the system under exertional conditions, and reassess after clinical or training changes. A practical approach to athlete-specific ICD programming is summarized in Table 4.
Table 4.
Athlete-specific implantable cardioverter-defibrillator programming and follow-up considerations.
7. Special Situations
Several clinical scenarios require additional caution when applying a return-to-sport approach to athletes with ICDs. These situations do not necessarily mandate restriction, but they often require more granular counseling, closer follow-up, and clearer boundaries around participation.
Risk differs substantially by underlying disease. In arrhythmogenic cardiomyopathy (ACM), exercise itself may accelerate disease progression and worsen the arrhythmic substrate, so the presence of an ICD does not remove the rationale for exercise restriction that exists independent of shock risk. Genotype-specific risk further refines this assessment: pathogenic variants in LMNA, FLNC, RBM20, PLN, and desmosomal genes are associated with disproportionately high arrhythmic risk that may not be fully captured by conventional phenotypic markers such as left ventricular ejection fraction, and the 2023 ESC cardiomyopathy guidelines incorporate genotype into contemporary risk stratification and ICD decision-making [32,33]. Brugada syndrome carries its own trigger-specific considerations, including fever and certain pharmacologic exposures, that are independent of exercise per se but warrant the same disease-specific counseling applied to other channelopathies. In catecholaminergic polymorphic ventricular tachycardia (CPVT) and long QT syndrome (LQTS), risk is closely tied to adrenergic state and trigger avoidance, and beta-blocker adherence and trigger-specific counseling remain central regardless of device therapy [9,10,34]. In hypertrophic cardiomyopathy (HCM), outflow tract dynamics and exertional hemodynamics inform risk beyond arrhythmia alone. Myocarditis carries a time-limited, higher risk window tied to active inflammation, though long-term fibrosis may occur. Congenital heart disease introduces anatomic and hemodynamic considerations that are independent of the ICD itself. These differences mean that return-to-sport planning must be disease-specific rather than device-specific, with the ICD treated as one component of a substrate-driven risk assessment rather than a substitute for it.
Pediatric and adolescent athletes require particular attention because return-to-sport decisions occur within the context of family dynamics, school policies, developmental stage, peer identity, and long-anticipated device exposure. Pediatric registry data are reassuring in that selected young athletes with ICDs have participated in sports without observed deaths, arrests, or arrhythmia-related injuries during sports participation; however, shocks and lead malfunction remain clinically important over time [7]. Counseling should include the athlete and family and address school emergency action plans, athletic trainer availability, medication adherence, psychosocial support, and the likelihood of future lead or generator interventions.
Elite and professional athletes present a different set of challenges. Their training intensity, public visibility, financial incentives, and external pressure to return may be substantially greater than those of recreational athletes. These factors can distort risk tolerance and complicate shared decision-making. Clinicians should distinguish the athlete’s own goals from expectations imposed by teams, sponsors, institutions, or family members. Documentation should be especially clear regarding the residual risks discussed, alternatives considered, emergency planning, and the athlete’s voluntary preference.
A 2026 retrospective analysis of sporting careers after ICD implantation in elite athletes offers descriptive insight into this population, though its media- and literature-based case identification carries substantial selection and ascertainment bias and should be interpreted as hypothesis-generating rather than definitive [35].
Return to sport after ICD therapy should be handled deliberately. An appropriate shock may indicate recurrent ventricular arrhythmia, progression of the underlying substrate, medication nonadherence, electrolyte disturbance, excessive exertional stress, or the need for ablation or medication adjustment. An inappropriate shock may reflect sinus tachycardia, supraventricular arrhythmia, oversensing, lead or sensing abnormalities, or programming issues. In either case, return to sport should generally be deferred until stored electrograms have been reviewed, the rhythm diagnosis has been confirmed, reversible triggers have been addressed, device function and programming have been reassessed, and the athlete’s emergency action plan has been updated.
These special situations are not exceptions to the return-to-sport framework. They are scenarios in which the structure must be applied with greater specificity. The central question remains whether the athlete can participate with an acceptable residual risk after the substrate, device system, programming strategy, sport environment, emergency plan, and follow-up structure have been deliberately addressed.
8. Future Directions
Future research should move beyond the broad question of whether selected athletes with ICDs can participate in sport. The next phase of evidence should define which athletes can participate, in which sports, with which device systems, under which programming strategies, and with what emergency-planning infrastructure. The original ICD Sports Registry established the foundation for contemporary return-to-sport counseling, but modern practice has evolved substantially. Athletes are now considered for lead-sparing systems, programmed with contemporary shock-reduction strategies, managed through remote monitoring, and counseled within a shared decision-making framework that must account for sport-specific hazards and patient values.
Contemporary data are particularly needed for lead-sparing ICD systems. S-ICDs are attractive for many young and active patients because they avoid transvenous leads, yet most prospective athlete data were generated in transvenous ICD populations. Future studies, such as the SPORT S-ICD study, should determine how S-ICD sensing performs during high-intensity exercise, repetitive upper-extremity activity, posture changes, direct impact, and sport-specific body positions [18]. The ongoing ORCCA registry also includes athletes with ICDs that may inform the discussion [36].
EV-ICD systems represent another important research priority. These systems may offer a potential middle ground between transvenous and subcutaneous platforms by avoiding intravascular leads while preserving selected pacing capabilities, including ATP. Long-term pivotal data support EV-ICD performance and safety in broader ICD populations, but athlete-specific outcomes remain limited [24].
Future registries should also deliberately include populations and sports that remain underrepresented. These include pediatric and adolescent athletes, female athletes, elite and professional athletes, athletes with adult congenital heart disease [37], athletes with arrhythmogenic cardiomyopathy [34], and athletes participating in collision, water, motor, remote, or other high-consequence sports. These groups are clinically important because risk is shaped not only by arrhythmia probability, but also by developmental stage, anatomy, disease progression, external pressure to participate, device durability, and the consequences of transient impairment in a specific environment.
9. Conclusions
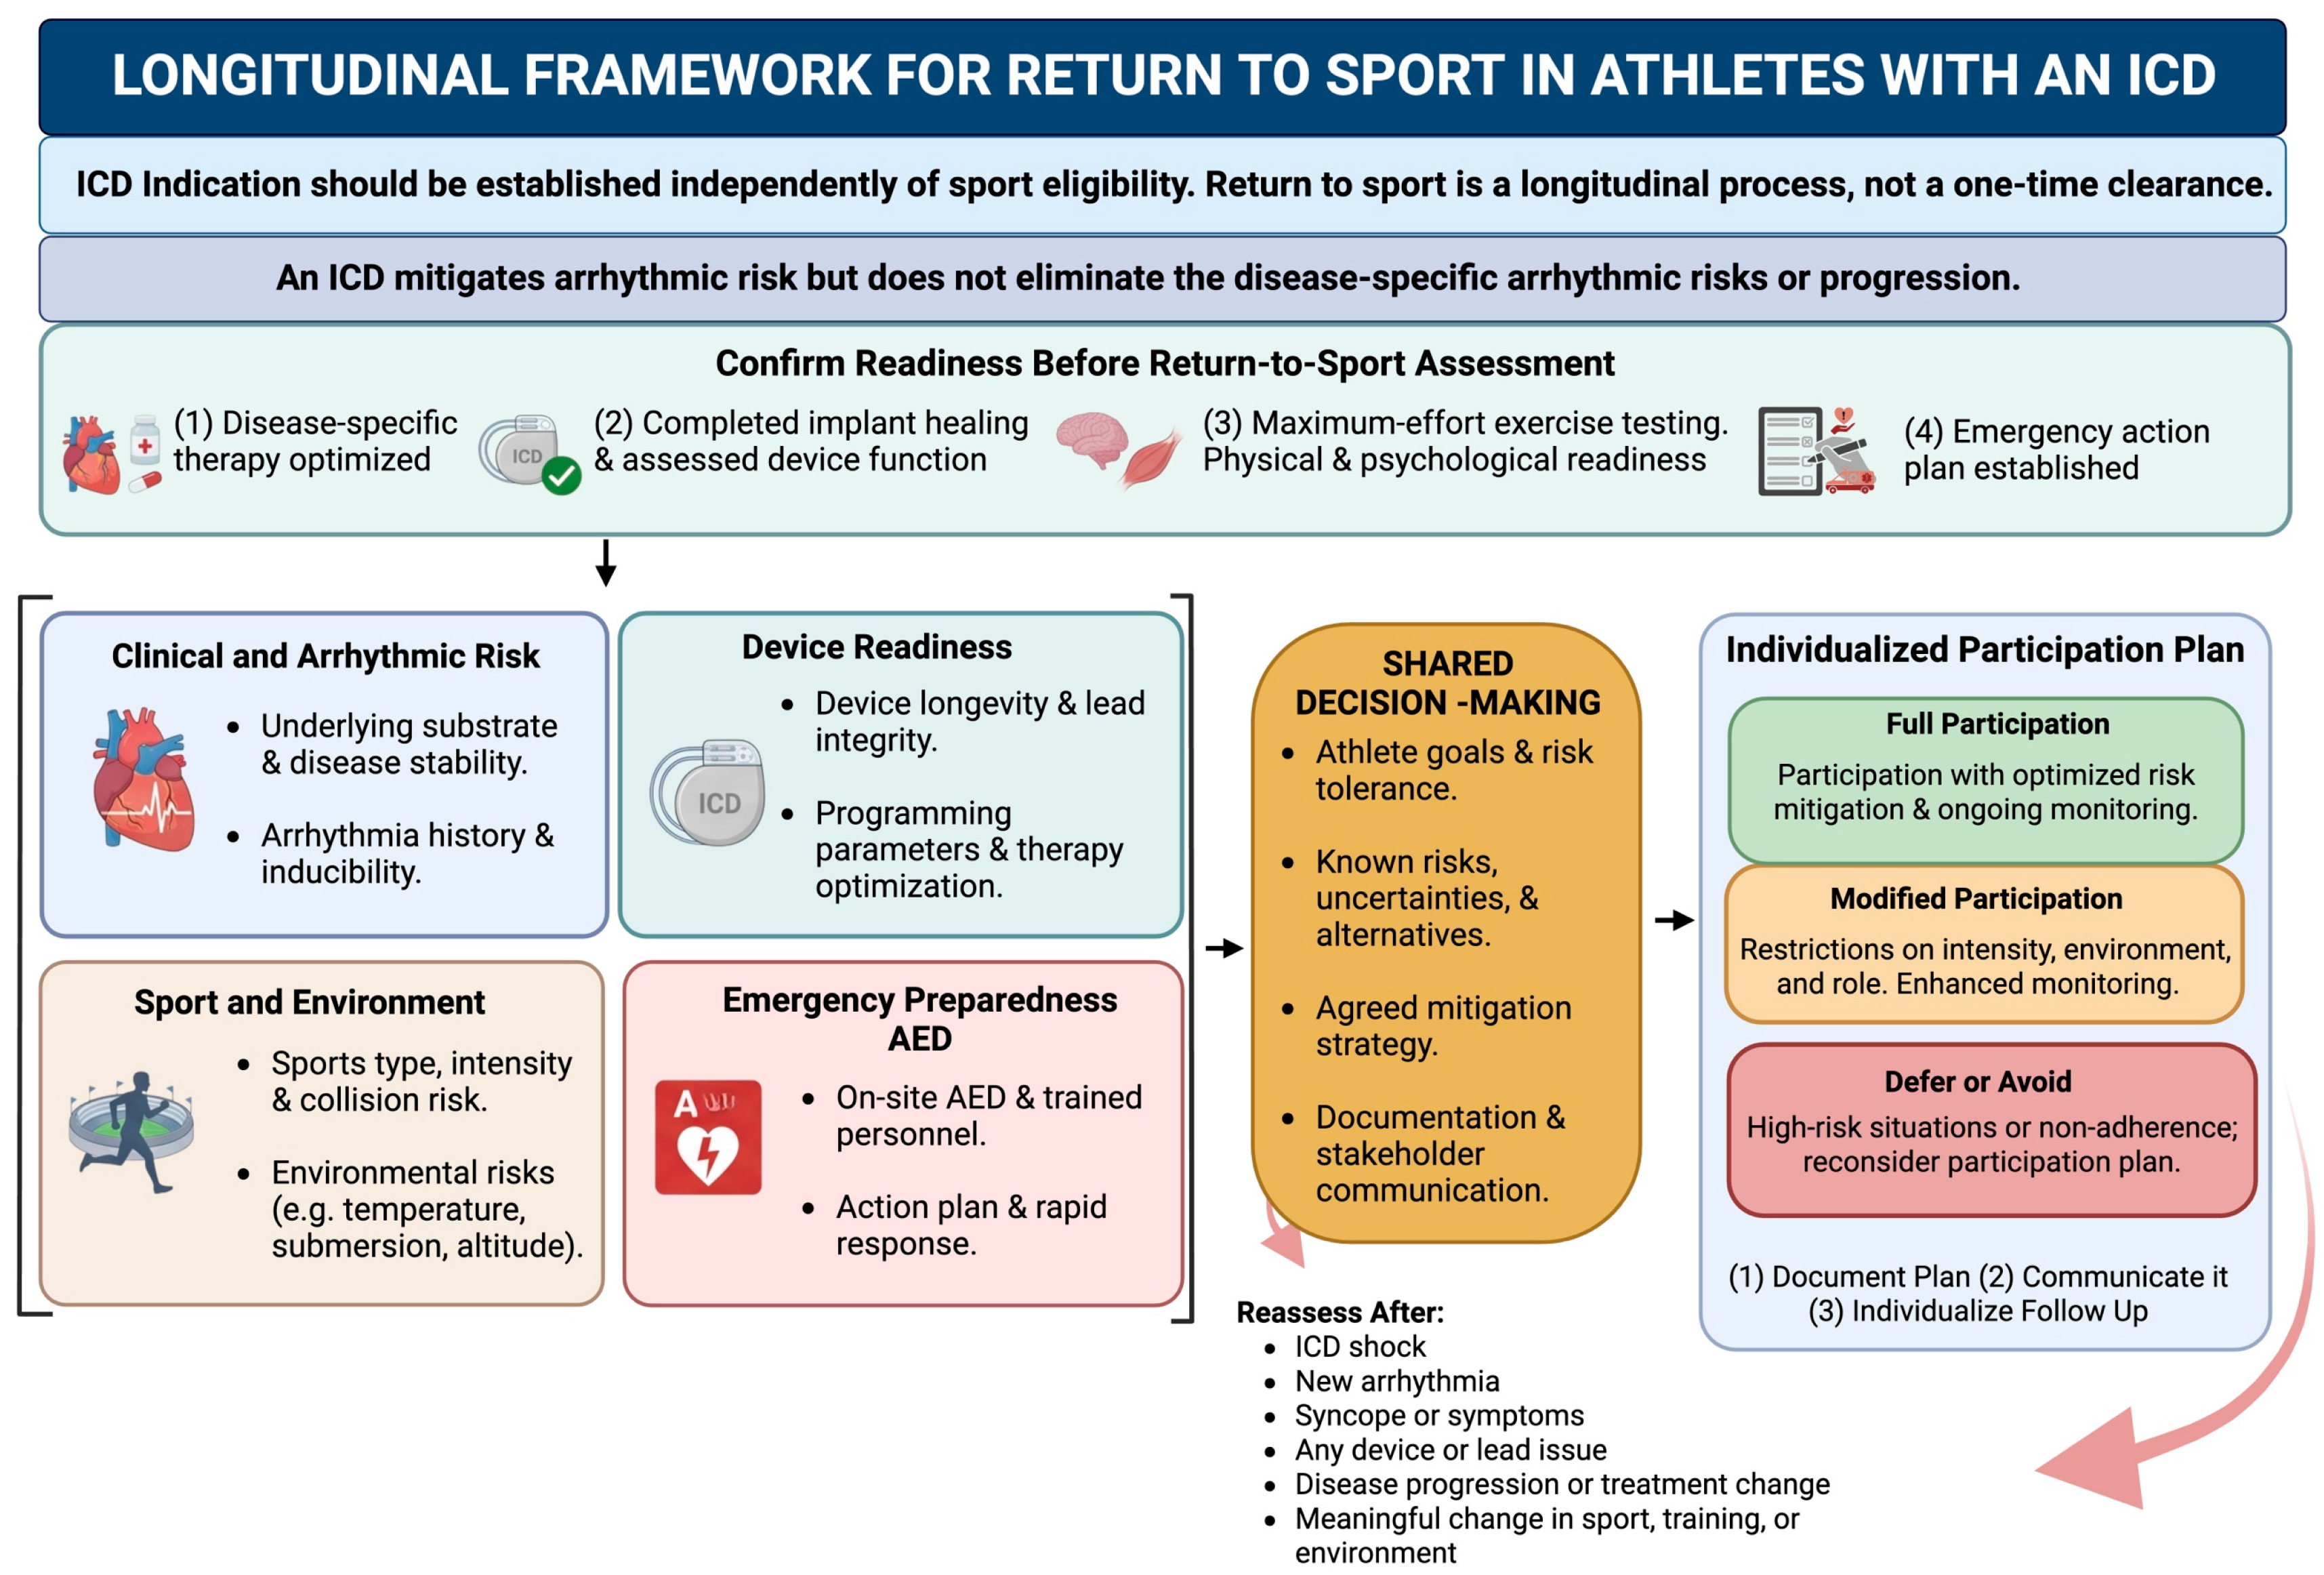
The presence of an ICD should no longer be viewed as an automatic exclusion from vigorous or competitive sport. Contemporary registry data and expert consensus support an individualized approach in which selected athletes with ICDs may participate when the underlying substrate, device system, programming strategy, sport environment, emergency planning, and follow-up structure are deliberately addressed [5,6,7,8,9]. However, these data should not be interpreted as an absence of risk. ICD therapies occur, inappropriate shocks remain clinically relevant, device durability matters, and some sport environments carry consequences that extend beyond the arrhythmia itself.
The modern care of athletes with ICDs, therefore, requires more than a clearance decision. The decision to implant an ICD stays anchored to the underlying arrhythmic diagnosis, independent of any athletic ambition. Device selection should account for pacing needs, ATP, anatomy, age, sport exposure, and long-term hardware considerations. Programming should be informed by exercise physiology and reassessed after shocks, symptoms, medication changes, ablation, or changes in training intensity. Risk mitigation should include emergency action planning, access to automated external defibrillators, post-shock protocols, trauma prevention, remote monitoring, and structured follow-up.
Shared decision-making sits at the center of this process, but it only works if it stays rigorous, a real conversation about risk rather than a formality on the way to yes. Clinicians should communicate known risks, acknowledge uncertainty, document the athlete’s goals and values, and define practical steps to reduce modifiable hazards. The goal is not to make sport risk-free, but to help selected athletes participate with the lowest achievable and most transparent residual risk.
Author Contributions
Conceptualization, D.S.D. and J.M.P.; writing—original draft preparation, D.S.D. and J.M.P.; writing—review and editing, D.S.D. and J.M.P.; supervision, J.M.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| AED | Automated external defibrillator |
| ATP | Antitachycardia pacing |
| CRT | Cardiac resynchronization therapy |
| EAP | Emergency action plan |
| EV-ICD | Extravascular implantable cardioverter-defibrillator |
| HCM | Hypertrophic cardiomyopathy |
| ICD | Implantable cardioverter-defibrillator |
| SCA | Sudden cardiac arrest |
| SCD | Sudden cardiac death |
| SDM | Shared decision-making |
| S-ICD | Subcutaneous implantable cardioverter-defibrillator |
| TV-ICD | Transvenous implantable cardioverter-defibrillator |
| VF | Ventricular fibrillation |
| VT | Ventricular tachycardia |
References
- Maron, B.J.; Zipes, D.P. Introduction: Eligibility recommendations for competitive athletes with cardiovascular abnormalities—General considerations. J. Am. Coll. Cardiol. 2005, 45, 1318–1321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maron, B.J.; Zipes, D.P.; Kovacs, R.J. Eligibility and disqualification recommendations for competitive athletes with cardiovascular abnormalities: Preamble, principles, and general considerations: A scientific statement from the American Heart Association and American College of Cardiology. J. Am. Coll. Cardiol. 2015, 66, 2343–2349. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zipes, D.P.; Link, M.S.; Ackerman, M.J.; Kovacs, R.J.; Myerburg, R.J.; Estes, N.A.M. Eligibility and disqualification recommendations for competitive athletes with cardiovascular abnormalities: Task Force 9: Arrhythmias and conduction defects: A scientific statement from the American Heart Association and American College of Cardiology. J. Am. Coll. Cardiol. 2015, 66, 2412–2423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pelliccia, A.; Sharma, S.; Gati, S.; Bäck, M.; Börjesson, M.; Caselli, S.; Collet, J.-P.; Corrado, D.; Drezner, J.A.; Halle, M.; et al. 2020 ESC Guidelines on sports cardiology and exercise in patients with cardiovascular disease. Eur. Heart J. 2021, 42, 17–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lampert, R.; Olshansky, B.; Heidbuchel, H.; Lawless, C.; Saarel, E.; Ackerman, M.; Calkins, H.; Estes, N.M.; Link, M.S.; Maron, B.J.; et al. Safety of sports for athletes with implantable cardioverter-defibrillators: Results of a prospective, multinational registry. Circulation 2013, 127, 2021–2030. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lampert, R.; Olshansky, B.; Heidbuchel, H.; Lawless, C.; Saarel, E.; Ackerman, M.; Calkins, H.; Estes, N.M.; Link, M.S.; Maron, B.J.; et al. Safety of sports for athletes with implantable cardioverter-defibrillators: Long-term results of a prospective multinational registry. Circulation 2017, 135, 2310–2312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saarel, E.V.; Law, I.; Berul, C.I.; Ackerman, M.J.; Kanter, R.J.; Sanatani, S.; Cohen, M.I.; Berger, S.; Fischbach, P.S.; Burton, D.A.; et al. Safety of sports for young patients with implantable cardioverter-defibrillators: Long-term results of the multinational ICD Sports Registry. Circ. Arrhythm. Electrophysiol. 2018, 11, e006305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heidbuchel, H.; Willems, R.; Jordaens, L.; Olshansky, B.; Carre, F.; Lozano, I.F.; Wilhelm, M.; Müssigbrodt, A.; Huybrechts, W.; Morgan, J.; et al. Intensive recreational athletes in the prospective multinational ICD Sports Safety Registry: Results from the European cohort. Eur. J. Prev. Cardiol. 2019, 26, 764–775. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lampert, R.; Chung, E.H.; Ackerman, M.J.; Arroyo, A.R.; Darden, D.; Deo, R.; Dolan, J.; Etheridge, S.P.; Gray, B.R.; Harmon, K.G.; et al. 2024 HRS expert consensus statement on arrhythmias in the athlete: Evaluation, treatment, and return to play. Heart Rhythm 2024, 21, e151–e252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, J.H.; Baggish, A.L.; Levine, B.D.; Ackerman, M.J.; Day, S.M.; Dineen, E.H.; Guseh, J.S.; La Gerche, A.; Lampert, R.; Martinez, M.W.; et al. Clinical Considerations for Competitive Sports Participation for Athletes With Cardiovascular Abnormalities: A Scientific Statement From the American Heart Association and American College of Cardiology. Circulation 2025, 151, e716–e761. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eri, R.R.; Zahrani, S.; Andriono, P.; Balweel, H.; Tafriend, N.A.; Harsoyo, A. Return-to-play in athletes with transvenous and subcutaneous implantable cardiac defibrillator: A meta-analysis. J. Arrhythmia 2025, 41, e70131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gasperetti, A.; Schiavone, M.; Vogler, J.; Compagnucci, P.; Laredo, M.; Breitenstein, A.; Gulletta, S.; Martinek, M.; Kaiser, L.; Lavalle, C.; et al. Long-term performance of subcutaneous implantable defibrillators in athletes: A multicenter, real-world analysis of sport activities from the iSUSI registry. Heart Rhythm 2025, 22, 1782–1789. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsieh, P.N.; Kontopidis, A.; Burr, J.; Stewart, K.; Churchill, T.W.; Guseh, J.S.; Chung, E.H. Exercise-guided programming of a subcutaneous implantable cardioverter-defibrillator in an athlete. Hear. Case Rep. 2025, 11, 1257–1261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Earle, W.; Cambron, J.C.; Petek, B.J.; Chung, E.H.; Henrikson, C.A.; Phan, F. Hitting a new PR: Extravascular ICD implant in a professional powerlifter. Hear. Case Rep. 2025, 11, 1267–1270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zeppenfeld, K.; Tfelt-Hansen, J.; de Riva, M.; Winkel, B.G.; Behr, E.R.; Blom, N.A.; Charron, P.; Corrado, D.; Dagres, N.; de Chillou, C.; et al. 2022 ESC Guidelines for the management of patients with ventricular arrhythmias and the prevention of sudden cardiac death. Eur. Heart J. 2022, 43, 3997–4126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Link, M.S.; Sullivan, R.M.; Olshansky, B.; Cannom, D.; Berul, C.I.; Hauser, R.G.; Heidbuchel, H.; Jordaens, L.; Krahn, A.D.; Morgan, J.; et al. Implantable cardioverter defibrillator lead survival in athletic patients. Circ. Arrhythm. Electrophysiol. 2021, 14, e009344. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Francia, P.; Ziacchi, M.; Migliore, F.; De Filippo, P.; Dello Russo, A.; Viani, S.; Rapacciuolo, A.; Falasconi, G.; Adduci, C.; Bisignani, G.; et al. Subcutaneous Implantable Defibrillators in Young Patients: Arrhythmias, Complications, and Physical Activity. Circ. Arrhythm. Electrophysiol. 2025, 18, e013365. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chorin, E.; Lampert, R.; Bijsterveld, N.R.; Knops, R.E.; Wilde, A.A.; Heidbuchel, H.; Krahn, A.; Goldenberg, I.; Rosso, R.; Viskin, D.; et al. Safety of Sports for Patients with Subcutaneous Implantable Cardioverter Defibrillator (SPORT S-ICD): Study rationale and protocol. Heart Rhythm O2 2024, 5, 182–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Friedman, P.; Murgatroyd, F.; Boersma, L.V.A.; Manlucu, J.; O’Donnell, D.; Knight, B.P.; Clémenty, N.; Leclercq, C.; Amin, A.; Merkely, B.P.; et al. Efficacy and safety of an extravascular implantable cardioverter-defibrillator. N. Engl. J. Med. 2022, 387, 1292–1302. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ommen, S.R.; Ho, C.Y.; Asif, I.M.; Balaji, S.; Burke, M.A.; Day, S.M.; Dearani, J.A.; Epps, K.C.; Evanovich, L.; Ferrari, V.A.; et al. 2024 AHA/ACC/AMSSM/HRS/PACES/SCMR guideline for the management of hypertrophic cardiomyopathy: A report of the American Heart Association/American College of Cardiology Joint Committee on Clinical Practice Guidelines. Circulation 2024, 149, e1239–e1311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knops, R.E.; Olde Nordkamp, L.R.A.; Delnoy, P.P.H.M.; Boersma, L.V.A.; Kuschyk, J.; El-Chami, M.F.; Bonnemeier, H.; Behr, E.R.; Brouwer, T.F.; Kääb, S.; et al. Subcutaneous or transvenous defibrillator therapy. N. Engl. J. Med. 2020, 383, 526–536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gold, M.R.; Lambiase, P.D.; El-Chami, M.F.; Knops, R.E.; Aasbo, J.D.; Bongiorni, M.G.; Russo, A.M.; Deharo, J.C.; Burke, M.C.; Dinerman, J.; et al. Primary results from the Understanding Outcomes With the S-ICD in Primary Prevention Patients With Low Ejection Fraction (UNTOUCHED) trial. Circulation 2021, 143, 7–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Healey, J.S.; Krahn, A.D.; Bashir, J.; Amit, G.; Philippon, F.; McIntyre, W.F.; Tsang, B.; Joza, J.; Exner, D.V.; Birnie, D.H.; et al. Perioperative safety and early patient and device outcomes among subcutaneous versus transvenous implantable cardioverter defibrillator implantations: A randomized, multicenter trial. Ann. Intern. Med. 2022, 175, 1658–1665. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Friedman, P.; Murgatroyd, F.; Boersma, L.V.A.; Manlucu, J.; O’Donnell, D.; Knight, B.P.; Leclercq, C.; Amin, A.; Merkely, B.; Birgersdotter-Green, U.M.; et al. Performance and safety of the extravascular implantable cardioverter-defibrillator through long-term follow-up: Final results from the pivotal study. Circulation 2025, 151, 322–332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moss, A.J.; Schuger, C.; Beck, C.A.; Brown, M.W.; Cannom, D.S.; Daubert, J.P.; Estes, N.M.I.; Greenberg, H.; Hall, W.J.; Huang, D.T.; et al. Reduction in inappropriate therapy and mortality through ICD programming. N. Engl. J. Med. 2012, 367, 2275–2283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gasparini, M.; Proclemer, A.; Klersy, C.; Kloppe, A.; Lunati, M.; Ferrer, J.B.M.; Hersi, A.; Gulaj, M.; Wijfels, M.C.E.F.; Santi, E.; et al. Effect of long-detection interval vs standard-detection interval for implantable cardioverter-defibrillators on antitachycardia pacing and shock delivery: The ADVANCE III randomized clinical trial. JAMA 2013, 309, 1903–1911. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Auricchio, A.; Schloss, E.J.; Kurita, T.; Meijer, A.; Gerritse, B.; Zweibel, S.; AlSmadi, F.M.; Leng, C.T.; Sterns, L.D. Low inappropriate shock rates in patients with single- and dual/triple-chamber implantable cardioverter-defibrillators using a novel suite of detection algorithms: PainFree SST trial primary results. Heart Rhythm 2015, 12, 926–936. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilkoff, B.L.; Fauchier, L.; Stiles, M.K.; Morillo, C.A.; Al-Khatib, S.M.; Almendral, J.; Aguinaga, L.; Berger, R.D.; Cuesta, A.; Daubert, J.P.; et al. 2015 HRS/EHRA/APHRS/SOLAECE expert consensus statement on optimal implantable cardioverter-defibrillator programming and testing. Heart Rhythm 2016, 13, e50–e86. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Olshansky, B.; Atteya, G.; Cannom, D.; Heidbuchel, H.; Saarel, E.V.; Anfinsen, O.G.; Cheng, A.; Gold, M.R.; Müssigbrodt, A.; Patton, K.K.; et al. Competitive athletes with implantable cardioverter-defibrillators—How to program? Data from the Implantable Cardioverter-Defibrillator Sports Registry. Heart Rhythm 2019, 16, 581–587. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Drezner, J.A.; Courson, R.W.; Roberts, W.O.; Mosesso, V.N.; Link, M.S.; Maron, B.J. Inter-Association Task Force recommendations on emergency preparedness and management of sudden cardiac arrest in high school and college athletic programs: A consensus statement. J. Athl. Train. 2007, 42, 143–158. [Google Scholar] [PubMed]
- Pelto, H.F.; Drezner, J.A. Design and implementation of an emergency action plan for sudden cardiac arrest in sport. J. Cardiovasc. Transl. Res. 2020, 13, 331–338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tetaj, N.; Segreti, A.; Ferro, A.; Ligorio, V.; Spagnolo, A.; Grigioni, F. High-Risk Cardiomyopathy Genotypes and Arrhythmic Risk: LMNA, FLNC, RBM20, PLN and Desmosomal Genes in the ESC 2023 Era. Genes 2026, 17, 370. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arbelo, E.; Protonotarios, A.; Gimeno, J.R.; Arbustini, E.; Barriales-Villa, R.; Basso, C.; Bezzina, C.R.; Biagini, E.; A Blom, N.; A de Boer, R.; et al. 2023 ESC Guidelines for the management of cardiomyopathies. Eur. Heart J. 2023, 44, 3503–3626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Towbin, J.A.; McKenna, W.J.; Abrams, D.J.; Ackerman, M.J.; Calkins, H.; Darrieux, F.C.C.; Daubert, J.P.; de Chillou, C.; DePasquale, E.C.; Desai, M.Y.; et al. 2019 HRS expert consensus statement on evaluation, risk stratification, and management of arrhythmogenic cardiomyopathy. Heart Rhythm 2019, 16, e301–e372. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vecchiato, M.; Egger, F.; Palermi, S. Sporting Careers After ICD Implantation in Elite Athletes. J. Cardiovasc. Dev. Dis. 2026, 13, 97. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moulson, N.; Petek, B.J.; Ackerman, M.J.; Churchill, T.W.; Day, S.M.; Kim, J.H.; Kliethermes, S.A.; Lampert, R.; Levine, B.D.; Martinez, M.W.; et al. Rationale and Design of the ORCCA (Outcomes Registry for Cardiac Conditions in Athletes) Study. J. Am. Heart Assoc. 2023, 12, e029052. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gurvitz, M.; Krieger, E.V.; Fuller, S.; Davis, L.L.; Kittleson, M.M.; Aboulhosn, J.A.; Bradley, E.A.; Buber, J.; Daniels, C.J.; Dimopoulos, K.; et al. 2025 ACC/AHA/HRS/ISACHD/SCAI Guideline for the Management of Adults with Congenital Heart Disease: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. J. Am. Coll. Cardiol. 2026, 87, 822–976. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.