Skip to Content
You are currently on the new version of our website. Access the old version .
  • 4.8
    Impact Factor
  • 9.0
    CiteScore
  • 18 days
    Submission to First Decision
  • 3 days
    Acceptance to Publication

Cancers

Cancers is a peer-reviewed, open access journal of oncology published semimonthly online. The North-East German Society for Gynecological Oncology (NOGGO), Irish Association for Cancer Research (IACR), Spanish Association for Cancer Research (ASEICA), Biomedical Research Centre (CIBM), British Neuro-Oncology Society (BNOS) and more are affiliated with Cancers and their members receive a discount on the article processing charges.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (38,021)

  • Article
  • Open Access

Genes encoding BAH-domain proteins play important roles in many physiological and pathological cellular processes via the recognition of methylated substrates. We systematically analyzed the transcription levels of these genes, as well as their association with clinical and molecular features, in 31 cancer types. Our analysis revealed the potential prognostic value of BAH-containing genes in many cancers, notably that high levels of ORC1 expression are significantly associated with both shorter overall and disease-free survival in adrenocortical carcinoma, brain lower grade glioma, liver hepatocellular carcinoma, and sarcoma. We further observed that these tumors with high levels of ORC1 share several commonalities independently of their tissue of origin. High levels of ORC1 expression are notably associated with pathways related to cell proliferation and pluripotency-related networks, as well as mutation burden, chromosomal alterations, and aneuploidy, to different extents. We further identified a set of common master and upstream molecular regulators in tumors with high ORC1 expression in these different tumor types as well as computationally predicted therapeutic compounds. We thus provide a resource focused on BAH-containing genes that may help distinguish tumors with poor outcomes while also highlighting mechanistic, prognostic, and therapeutic features across different cancer types.

Cancers

14 November 2026

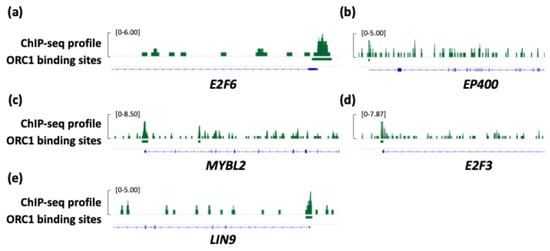
ChIP-sequencing profiles of ORC1 in HeLa cells at the promoter of several “Upstream Regulators”. On each panel (a–e) the ORC1 ChIP-seq profile (in green), ORC1 binding sites (reported in Dellino et al.; green bar) and the gene (in blue) are indicated.
  • Review
  • Open Access

Receptor tyrosine kinase (RTK) signaling is a major driver of oncogenesis and an important target in precision oncology. However, the presence of an oncogenic RTK alteration does not necessarily confer sustained functional dependency on the affected receptor or predict a durable therapeutic response. RTK-targeted therapy can trigger early adaptive signaling responses and, under continued therapeutic selection pressure, promote acquired resistance through compensatory pathway activation, secondary genetic alterations, phenotypic plasticity, and metabolic reprogramming. These processes are further shaped by receptor trafficking, intratumor heterogeneity, and the tumor microenvironment. Although individual resistance mechanisms are increasingly understood, their integration into a unified model of RTK dependency and tumor evolution remains incomplete. Here, we propose a multiscale framework integrating oncogenic alterations, functional signaling dependencies, and their evolution under therapeutic selection pressure. We examine how structural biology, functional genomics, multi-omics, and longitudinal biomarker profiling can characterize RTK activity, functional dependency and emerging vulnerabilities across molecular, cellular, and spatial contexts. We further discuss their potential to inform adaptive therapeutic strategies. This framework positions RTK dependency as a dynamic, context-dependent state rather than an invariant consequence of tumor genotype, highlighting the need to distinguish oncogenic driver status from functional dependency. Integrating genomic, functional, and longitudinal assessments may provide a basis for improved characterization of therapeutic response, evolving resistance, and emerging vulnerabilities in RTK-directed precision oncology.

Cancers

14 November 2026

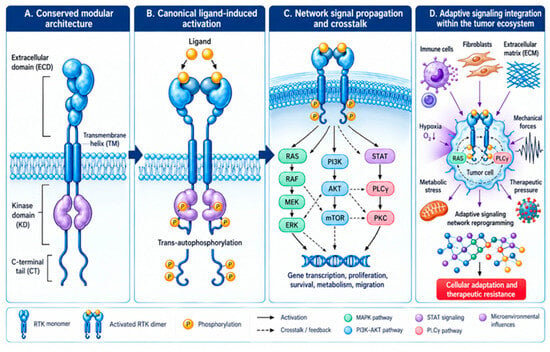
Modular architecture and conformational regulation of receptor tyrosine kinases (RTKs). RTKs comprise an extracellular ligand-binding domain, a single-pass transmembrane helix, and an intracellular tyrosine kinase domain with regulatory C-terminal tyrosine residues (A). Ligand engagement promotes receptor dimerization or stabilizes pre-existing dimers (B), triggering conformational rearrangements, asymmetric kinase activation, and trans-autophosphorylation that generate phosphotyrosine (pY) docking sites for Src homology 2 (SH2)- and phosphotyrosine-binding (PTB)-domain-containing signaling proteins (C). These signaling complexes recruit and activate interconnected downstream pathways, including RAS–RAF–MAPK, PI3K–AKT, and PLCγ-associated signaling, which interact through signaling crosstalk to regulate cellular proliferation, survival, differentiation, migration, and metabolism. Within the tumor ecosystem (D), RTK-associated signaling is influenced by multiple microenvironmental and therapeutic inputs, including signals from immune cells and fibroblasts, extracellular matrix (ECM) interactions, hypoxia, mechanical forces, metabolic stress, and therapeutic pressure. These diverse inputs converge on tumor cells and are associated with adaptive signaling network reprogramming, involving signaling nodes such as RAS and PLCγ, ultimately contributing to cellular adaptation and therapeutic resistance. Receptor internalization, endosomal signaling, recycling, and degradation provide additional levels of spatial and temporal regulation of RTK activity. Rather than existing as static molecular switches, RTKs occupy dynamic conformational states shaped by ligand engagement, receptor organization, and cellular context. This structural plasticity contributes to ligand- and context-dependent signaling and can influence inhibitor binding, therapeutic sensitivity, and adaptive responses to targeted therapy. Parts of this figure were created using BioRender.com.
  • Article
  • Open Access

Background/Objectives: We evaluated the association between early alpha-fetoprotein (AFP) decline and documented disease control during first-line immune checkpoint inhibitor (ICI)-based therapy for unresectable hepatocellular carcinoma (HCC). Methods: This retrospective health-system cohort included treatment initiation during 2020–2026. Eligibility required an exact positive baseline AFP, classifiable AFP measurements during days 14–56, and documented response. The primary exposure was any ≥20% AFP decline; ≥50% was a sensitivity threshold. Response was abstracted from routine imaging reports and oncologist documentation without independent RECIST reassessment. The primary Firth logistic model adjusted for age, performance status, macrovascular invasion, extrahepatic disease, and log baseline AFP. Secondary response, subgroup, and day-56 landmark survival analyses were exploratory. Results: Of 527 distinct patients, 392 met treatment/period/setting criteria and 167 (42.6%) entered analysis. Disease control occurred in 88/167 (52.7%); 68/167 (40.7%) had ≥20% decline. The primary adjusted association was an OR of 3.00 (95% CI 1.40–6.75; p = 0.004; n = 156), compared with an unadjusted OR of 2.29 (95% CI 1.21–4.33; p = 0.011; n = 167). At ≥50%, the adjusted disease-control association was an OR of 3.65 (95% CI 1.46–9.81; p = 0.005; n = 155). The first-draw sensitivity supported the association, whereas the day-21–35 analysis was inconclusive (p = 0.082). The response-after-day-56 analysis included 87 patients. Adjusted objective-response associations differed by threshold (p = 0.002 at ≥20%; p = 0.183 at ≥50%). Conclusions: Early AFP decline was associated with documented disease control among selected patients with reassessment data. Selection, temporal overlap, and potential response misclassification preclude claims of prospective predictive utility. Exploratory survival findings do not establish surrogacy.

Cancers

14 November 2026

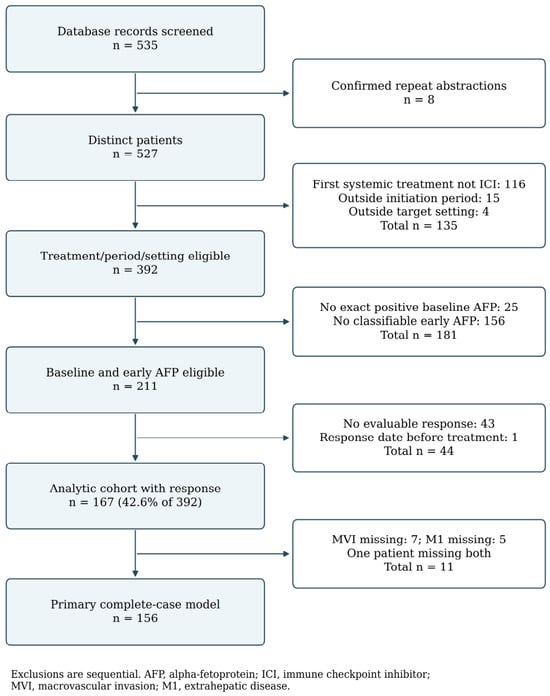
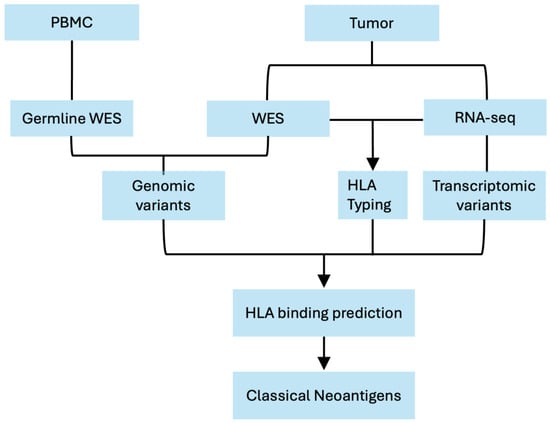
Patient selection and analytic populations. Sequential, mutually exclusive exclusions reduced 392 treatment/period/setting-eligible patients to 167 patients with classifiable AFP and an evaluable response (42.6%). Eleven additional patients lacked MVI and/or M1 for the primary adjusted model; one lacked both. AFP, alpha-fetoprotein; ICI, immune checkpoint inhibitor; MVI, macrovascular invasion; M1, extrahepatic disease.
  • Article
  • Open Access

Background: FoxP3 and programmed cell death protein 1 (PD-1) are immunoregulatory markers involved in the tumor microenvironment (TME) of Hodgkin lymphoma. Their prognostic significance in classical Hodgkin lymphoma (cHL) remains controversial. Objective: This study aimed to evaluate the prognostic significance of FoxP3- and PD-1-positive immune cells in cHL patients in an Ethiopian cohort. Methods: Clinical records of 68 consecutive patients diagnosed with cHL between 2015 and 2019 were retrospectively reviewed, with follow-up for up to 8 years. Tissue microarray sections were stained for FoxP3 and PD-1 by immunohistochemistry, and positive immune cells were quantified using HALO 2.3 digital image analysis. Overall survival (OS) and event-free survival (EFS) were assessed using Kaplan–Meier analysis and Cox proportional hazards regression. Results: The 5-year overall survival (OS) and event-free survival (EFS) rates were 82.8% and 79.9%, respectively, while the corresponding 8-year rates were 78.6% and 63.1%. Patients in the high-risk modified International Prognostic Score (IPS) group had lower 8-year OS and EFS rates of 63.5% and 45.4%, respectively (p = 0.04). In univariate Cox regression, low lymphocyte count (≤0.6 × 10⁹/L) was associated with inferior OS (HR = 5.1, 95% CI: 1.2–23; p = 0.02) and EFS (HR = 4; 95% CI: 1.3–11.9.0; p = 0.014). High expression of FoxP3 (≥9%) and PD-1 (≥24.6%), defined as categorical variables, were associated with poorer OS, with HRs of 4.3 (95% CI: 1.2–15.7; p = 0.015) and 3.4 (95% CI: (1.1–10.6); p = 0.02), respectively. High-risk IPS (≥3) was associated with inferior OS and EFS (p = 0.04). In multivariable analysis, low lymphocyte count, high FoxP3, and high PD-1 remained significantly associated with poorer OS. Conclusions: High FoxP3 and PD-1 expression, and low lymphocyte count were associated with unfavorable overall survival. However, neither marker (PD1 nor FoxP3) when defined as a continuous variable was significantly associated with OS. These findings require validation in larger independent cohorts.

Cancers

14 November 2026

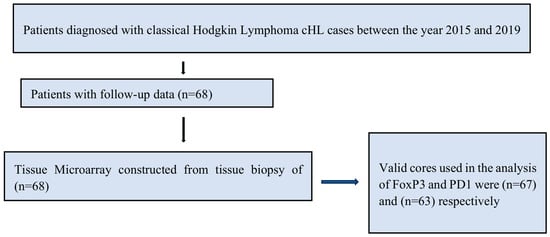
Flow chart of patients included in the study. cHL patients diagnosed between 2015 and 2019 at TASH.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
Cancers - ISSN 2072-6694