- Article

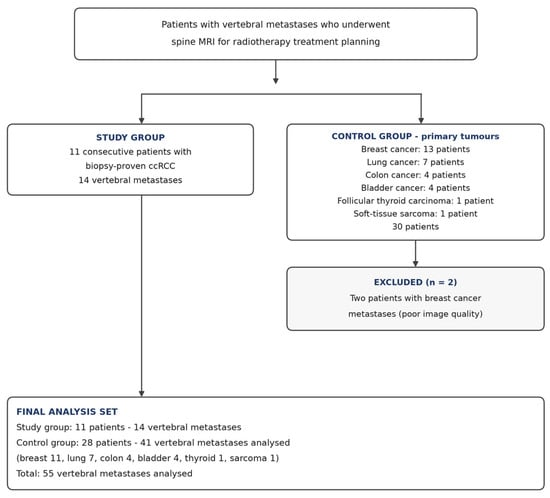
Background/Objective: To evaluate the diagnostic accuracy of spontaneous T1 hyperintensity relative to the spinal cord (signal intensity ratio [SIR] > 1) for identifying vertebral metastases from clear cell renal cell carcinoma (ccRCC) among vertebral metastases of other origins, and to assess the spinal cord as an internal reference standard, as an alternative to the conventional comparison with paravertebral muscle or the intervertebral disc. Methods: This retrospective, single-centre, case–control diagnostic accuracy study was conducted at University Hospital of Messina, Italy, between January 2017 and December 2023. Patients with vertebral metastases who underwent spine MRI for radiotherapy planning were included: 11 consecutive patients with biopsy-proven ccRCC (14 lesions) and 28 patients with metastases from other solid tumours (41 lesions; convenience sample). The index test was the lesion-to-spinal-cord SIR measured on unenhanced sagittal T1-weighted fast spin-echo images acquired at 1.5 T. Two blinded neuroradiologists independently performed the measurements; lesions were classified as hyperintense relative to the spinal cord using the prespecified threshold of SIR > 1. The flow-void sign was assessed as a secondary finding. Diagnostic accuracy was calculated on a per-lesion basis with 95% confidence intervals (CIs). Results: At the SIR > 1 threshold, both readers correctly classified 13/14 ccRCC metastases and 38/41 control metastases (13 true positives, 3 false positives, 1 false negative, and 38 true negatives). Sensitivity was 92.9% (95% CI, 68.5–98.7%), specificity was 92.7% (95% CI, 80.6–97.5%), and accuracy was 92.7%. The positive and negative likelihood ratios were 12.7 (95% CI, 4.2–38.1) and 0.077 (95% CI, 0.011–0.51), respectively. The area under the receiver operating characteristic curve was 0.960 (95% CI, 0.886–1.000) for reader 1 and 0.953 (95% CI, 0.873–1.000) for reader 2. Categorical inter-reader agreement was perfect (55/55, 100%; Cohen’s kappa = 1.00). Continuous SIR measurements showed a concordance correlation coefficient of 0.896, a mean inter-reader difference of 0.003 SIR units, and no systematic bias (p > 0.9). The flow-void sign was present in 7/14 ccRCC lesions; it was not assessed in the control group. The three false-positive lesions originated from thyroid, breast, and lung cancers. Conclusions: In this preliminary series, T1 hyperintensity relative to the spinal cord was frequent in ccRCC vertebral metastases and uncommon in metastases from other tumours. Owing to the case–control design, non-consecutive controls, and small sample size, diagnostic accuracy may have been overestimated; validation in prospective, consecutive, multicentre cohorts is required.
14 November 2026