Skip to Content
You are currently on the new version of our website. Access the old version .
  • 2.9
    Impact Factor
  • 4.6
    CiteScore
  • 18 days
    Submission to First Decision
  • 3 days
    Acceptance to Publication

Medicina

Medicina is an international, peer-reviewed, open access journal covering all problems related to medicine, published monthly online. It is the official journal of the Lithuanian University of Health Sciences (LUHS). The Lithuanian Medical Association (LMA), Vilnius University, Rīga Stradiņš University, University of Latvia, and University of Tartu are affiliated with Medicina, serving as their official journal. Members of these organizations receive discounts on the article processing charges.
  • Open Access— free for readers, with article processing charges (APC) paid by authors or their institutions.
  • High Visibility: indexed within Scopus, SCIE (Web of Science), PubMed, MEDLINE, PMC, and other databases.
  • Journal Rank: JCR - Q1 (Medicine, General and Internal) / CiteScore - Q1 (General Medicine)
  • Rapid Publication: manuscripts are peer-reviewed and a first decision is provided to authors approximately 17.4 days after submission; acceptance to publication is undertaken in 2.8 days (median values for papers published in this journal in the first half of 2026).
  • Recognition of Reviewers: Reviewers whose reports are timely and of high quality receive an APC discount voucher for a future publication in an MDPI journal. Become a reviewer.

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (14,669)

  • Review
  • Open Access

Background and Objectives: Following FDA approval of cipepofol for adult surgical induction in May 2026, its comparative evidence requires interpretation within the approved indication and other studied settings. This comprehensive clinical review examines pharmacology, efficacy, cardiorespiratory effects, injection pain, recovery, and safety. Materials and Methods: PubMed/MEDLINE, CENTRAL, and ClinicalTrials.gov were searched from inception to 16 July 2026. Adult randomised comparisons were considered, with second-author assistance in sorting and verification. This structured narrative review was not a formal systematic review; no meta-analysis, formal risk-of-bias assessment, or GRADE assessment was undertaken. Results: The source set comprised 85 randomised comparative study reports: 41 in general anaesthesia, 40 in procedural or adjunct sedation, and four in ICU sedation. A single participant total is not presented because enrolment, eligible-arm, and analysed populations were not consistently defined. Pivotal trials demonstrated high protocol success, and directly reported comparisons showed less injection pain with cipepofol. Haemodynamic and respiratory findings varied by regimen, population, endpoint definition, and rescue practice. Recovery findings were mixed. Neurocognitive benefit, organ protection, mortality reduction, and rare-harm superiority were not established. Conclusions: Cipepofol is an effective hypnotic under the adult protocols evaluated. Following approval, clinical interpretation should distinguish surgical induction from maintenance, procedural sedation, and ICU applications. Potential tolerability advantages do not establish overall safety superiority or justify reduced monitoring.

Medicina

14 November 2026

Identification and selection of report records for this comprehensive clinical review. Counts describe the original structured-search workflow and the comparator correction, not independently repeated systematic-review screening. Report assessment used full texts, abstracts, or registry information as available. The visual format draws on PRISMA 2020 [13]. During revision, two background reports were excluded: Zhu et al. [21] and Ding et al. [22].
  • Article
  • Open Access

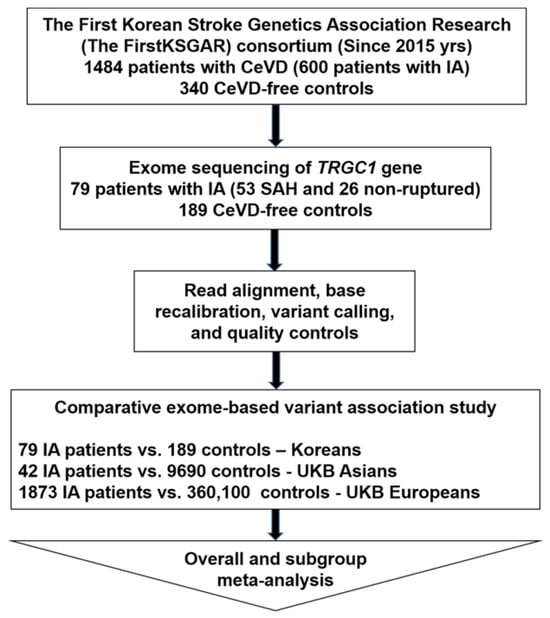
Background and Objectives: Although potential links exist between T-cell receptor (TR) genes and intracranial aneurysm (IA), the genetic contribution of TRGC1 variants to IA susceptibility remains unclear. We investigated TRGC1 variants using mutational association analysis in a Korean cohort and evaluated their associations in ancestry-stratified UK Biobank (UKB) populations, followed by cross-population meta-analysis. Materials and Methods: Targeted exome sequencing of TRGC1 (7p14.1) was performed in 79 IA patients and 189 controls from the FirstKSGAR cohort. Variants were also evaluated using UKB data from 42 IA patients and 9690 controls of Asian ancestry, and 1873 IA patients and 360,100 controls of European ancestry. Associations were assessed via multivariable logistic regression and inverse-variance weighted meta-analysis. Results: Two TRGC1 variants (rs2007081 and rs113809137) were available across all populations, showing no significant association with IA susceptibility individually (p > 0.05). In cross-population meta-analysis, pooled ORs were 0.99 (p = 0.8031) for rs2007081 and 1.03 (p = 0.4643) for rs113809137 (I2 = 0%). Asian-ancestry subgroup meta-analysis also showed no significant associations (pooled OR = 1.15, p = 0.4997 for rs2007081; pooled OR = 1.27, p = 0.2076 for rs113809137). Conclusions: The evaluated TRGC1 variants were not significantly associated with IA susceptibility, suggesting that rs2007081 and rs113809137 are unlikely to have major effects on IA risk. Larger studies are warranted to clarify these findings and determine whether other variants within the TR gene family contribute to IA susceptibility.

Medicina

14 November 2026

Study design and cohort selection for the exome-based variant association analysis of TRGC1 gene and intracranial aneurysm.
  • Review
  • Open Access

Aldosterone Synthase Inhibitors in Chronic Kidney Disease

  • Paula Polenus and
  • Sandra Karanović Štambuk

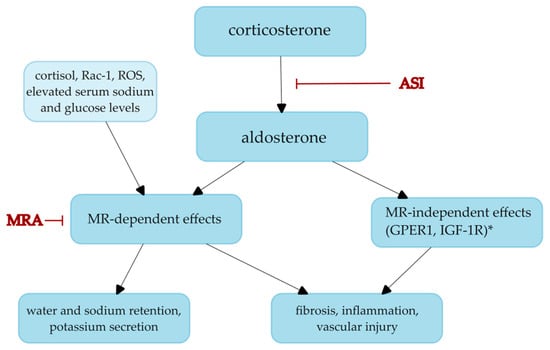
Chronic kidney disease (CKD) is a growing global health burden closely linked to diabetes, hypertension and increased cardiovascular risk. The persistent activation of the renin–angiotensin–aldosterone system contributes to disease progression. Aldosterone, acting through mineralocorticoid receptors (MRs), promotes sodium retention and blood pressure elevation, but also drives inflammation, fibrosis, albuminuria and structural remodeling in renal and cardiovascular tissues. Emerging evidence suggests additional MR-independent mechanisms and alternative pathways of MR activation, further complicating its pathophysiological role. Aldosterone synthase inhibitors (ASIs) have been developed to suppress aldosterone production upstream by targeting aldosterone synthase-CYP11B2. Second-generation agents including baxdrostat, lorundrostat and vicadrostat, demonstrate improved selectivity compared with earlier compounds and have advanced through a phase II clinical evaluation in patients with hypertension and CKD. Across studies, ASIs achieved effective aldosterone suppression, reductions in systolic blood pressure and favorable effects on albuminuria. However, hyperkalemia emerged as a clinically relevant safety concern, particularly in CKD populations, challenging the expectation of a clearly superior electrolyte profile compared with MR antagonists. The relative importance of excess aldosterone versus MR overactivation in CKD progression remains uncertain. While upstream inhibition is mechanistically attractive and may offer theoretical advantages, definitive evidence demonstrating reductions in hard renal and cardiovascular outcomes is lacking. The discontinuation of the phase III EASi-KIDNEY trial provides an important negative signal regarding vicadrostat in the studied setting. However, in the absence of complete published results, this discontinuation should not be interpreted as definitive evidence of treatment inefficacy or generalized to ASIs as a drug class. Once the results from the EASi-KIDNEY trial are published, together with the data from ongoing outcome-driven trials, the therapeutic value of ASIs will be better understood. At present, ASIs represent a scientifically rational but investigational strategy in CKD management, pending definitive confirmation of long-term efficacy and safety.

Medicina

14 November 2026

Schematic overview of aldosterone synthesis and downstream mineralocorticoid receptor (MR)-dependent and MR-independent effects, with pharmacologic targets. Aldosterone is synthesized from corticosterone via aldosterone synthase (CYP11B2), a step inhibited by aldosterone synthase inhibitors (ASIs). Once produced, aldosterone exerts biological effects through MR-dependent and potentially MR-independent pathways. MR-dependent effects include classical epithelial actions such as sodium and water retention with potassium secretion, as well as pro-inflammatory, pro-fibrotic, and vascular injury pathways in renal and cardiovascular tissues. Mineralocorticoid receptor antagonists (MRAs) block MR-mediated signaling. In addition to aldosterone, MR activation may occur through alternative stimuli, including cortisol, Rac1, reactive oxygen species (ROS), elevated serum sodium and hyperglycemia. * The existence and relative contribution of MR-independent effects of aldosterone remain incompletely defined (GPER1—G protein coupled estrogen receptor 1, IGF-1R-insulin-like growth factor-1 receptor).
  • Article
  • Open Access

Long-Term Kidney Outcomes in COVID-19 Survivors with and Without Acute Kidney Injury

  • Chairat Shayakul,
  • Charanya Nawarat and
  • Naparat Kaewkaukul

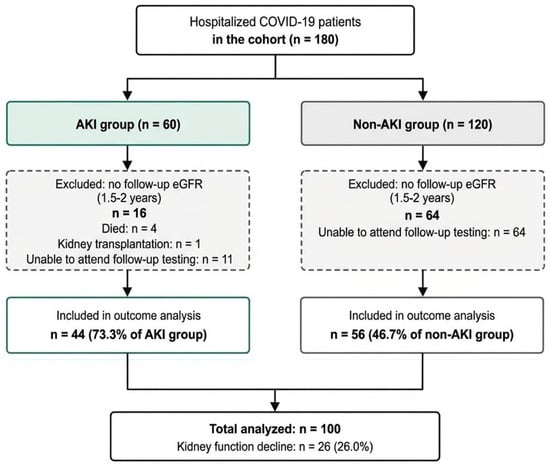
Background and Objectives: Acute kidney injury (AKI) is a common complication of COVID-19 and is associated with increased short-term mortality. However, long-term kidney outcomes among survivors remain incompletely characterized. Materials and Methods: We conducted a cohort study of hospitalized COVID-19 patients at a tertiary care university hospital, classifying them during admission according to the KDIGO AKI criteria. Survivors underwent follow-up assessment approximately 1.5–2 years post-discharge, which included laboratory evaluations and a structured questionnaire. This questionnaire collected patient-reported outcomes regarding post-discharge health worsening and any new medical diagnoses during the follow-up period. The primary outcome was kidney function decline (eGFR <60 mL/min/1.73 m2 together with a ≥25% decrease from discharge) among survivors with follow-up eGFR; all-cause mortality was analyzed separately. Associated factors were identified using modified Poisson regression models. Results: A total of 180 patients were included (60 with AKI and 120 without); kidney outcomes were analyzed in 100 patients with follow-up eGFR (44 and 56 respectively). Patients with AKI were older, had more comorbidities, and experienced more severe COVID-19. At a median follow-up of 1.65 years, 4 of 60 patients with AKI had died and one required kidney transplantation. Among the 100 analyzed patients, patient-reported worsening of overall health and newly diagnosed conditions did not differ significantly between groups. Kidney function decline occurred in 23 of 44 patients with AKI (52.3%) and 3 of 56 patients without AKI (5.4%); the AKI group also had lower follow-up eGFR and greater eGFR decline. In multivariable analysis, AKI remained independently associated with the primary outcome (adjusted RR 7.92, 95% CI 2.41–25.98; p < 0.001). Conclusions: Among COVID-19 survivors, AKI is associated with long-term kidney function decline and higher mortality. These findings support the need for structured post-discharge kidney monitoring in this high-risk population.

Medicina

14 November 2026

Study flowchart of patient selection and follow-up.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
Medicina - ISSN 1648-9144